
Last updated: 13 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Cryo-Lung Biopsy in India is typically planned at $1,200–$3,500 per cryobiopsy admission, with 1–2 nights as the stored stay guide. The range commonly covers the named pulmonologist, procedure suite, standard monitoring, sedation or anaesthesia, routine consumables and quoted ward care; CT or PET review, advanced devices, pathology, molecular testing, ICU and treatment after results may be separate. $5,000–$14,000 is the comparison reference.
Specialist HRCT and pathology review before and after biopsy are part of safe diagnostic use. Endotracheal or rigid access and controlled ventilation require theatre-level resources.
- India cost range
- $1,200–$3,500
- Typical starting point
- $1,200
- Typical hospital stay
- 1–2 nights
- Procedure time
- Often 60–120 minutes, plus anaesthetic setup, repeated haemostasis checks and post-biopsy imaging
- Recovery
- Cough, sore throat and small blood streaks can occur, but vigilance for delayed bleeding and pneumothorax is essential.
Major cost factors: ild multidisciplinary selection, general anaesthesia and airway, cryoprobes and gas system, fluoroscopy and blocker. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed procedural scope; complications and escalation; premium devices and consumables; advanced diagnostics; travel and ongoing care.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
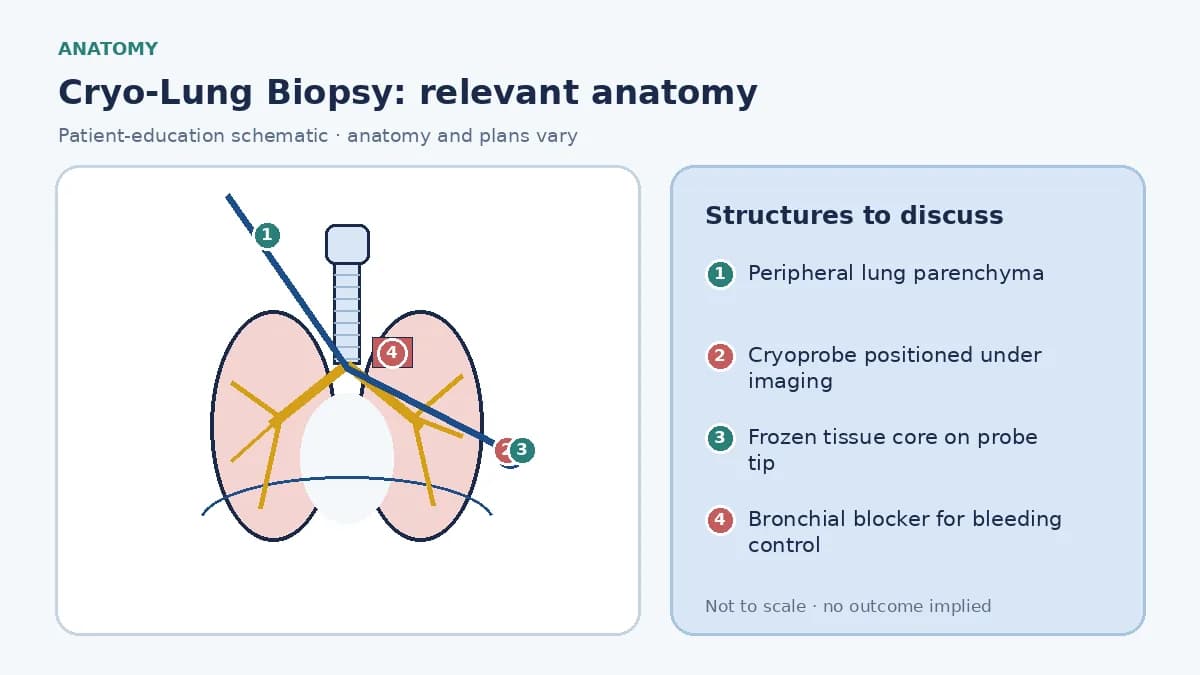
Under fluoroscopic guidance the probe is positioned a measured distance from the pleura in an HRCT-selected segment. Gas expansion cools the tip for a controlled freeze, binding a disc of lung to it; probe and bronchoscope are withdrawn together because the frozen core cannot pass through the channel. A pre-positioned bronchial blocker isolates the sampled lobe during bleeding control.
This slug owns parenchymal cryoprobe biopsy, not cryotherapy of an airway tumour. It is not simply a larger TBLB and should not be offered without fluoroscopy, blocker-based bleeding control and high-acuity rescue. Even large cores can be non-diagnostic, and multidisciplinary interpretation remains necessary.
This guide compares quotations; it cannot diagnose, choose a procedure or decide timing. A respiratory specialist must connect symptoms, imaging, physiology and laboratory findings and explain uncertainty.
What Is Cryo-Lung Biopsy?
Transbronchial lung cryobiopsy uses a flexible cryoprobe passed through a bronchoscope into peripheral lung, where rapid cooling freezes parenchyma onto the probe for en-bloc extraction. It yields larger, less-crushed tissue cores than forceps biopsy but carries important bleeding and pneumothorax risks.
When Might Cryo-Lung Biopsy Be Considered?
Cryobiopsy may be considered after multidisciplinary ILD review when HRCT, clinical and laboratory findings remain insufficient and tissue architecture is likely to change management. It requires adequate respiratory reserve and careful exclusion of disproportionate bleeding, pulmonary-hypertension or anaesthetic risk; observation without biopsy or surgical biopsy may be safer or more informative.
How the operation is performed, recovery and variations →
Cryo-Lung Biopsy cost in India
$1,200–$3,500 is the stored India planning range for transbronchial lung cryobiopsy, per cryobiopsy admission, and $5,000–$14,000 the stored self-pay comparison. Neither is a guaranteed package; changed technique, extra pathology, ICU support or a longer stay alters the amount.
A usable estimate names the clinician, campus, approach, cryoprobe, fluoroscopy and bronchial blocker, sedation or anaesthesia, oxygen, ward nights, specimen studies and follow-up, with professional, facility, device, imaging and laboratory lines separated.
Budget separately for flights, visa, insurance, transfers, companion, lodging, meals, home oxygen or equipment and local follow-up unless included.
Planning Range ≠ Final Hospital Quotation. Current imaging, respiratory reserve, oxygen needs and assessment by a named interventional pulmonologist in an experienced cryobiopsy and ILD programme come before technique, risks and a final offer are meaningful.
Planning range or quotation?
The $1,200–$3,500 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Cryo-Lung Biopsy package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Named respiratory consultation
Records and imaging review by the operating pulmonologist when explicitly listed.
Usually included
Pre-procedure assessment
Stated blood tests, ECG, oxygen assessment, urine tests and anaesthesia review; unlisted work-up is extra.
Usually included
Procedure suite and sedation
Bronchoscopy or procedure-room time, standard monitoring, sedation or anaesthesia and recovery care within scope.
Usually included
Quoted hospital stay
The stated day-care or ward category, routine oxygen, nursing and medicines for the listed nights.
Usually included
Standard specimen processing
Histopathology, cytology or microbiology only when itemized; molecular panels and special stains may be separate.
Usually included
Cryoprobe, fluoroscopy and bronchial blocker
The stated probe and cores, imaging guidance, blocker-based haemostasis and initial ILD pathology processing when listed.
May be charged separately
May be separate
Changed procedural scope
A diagnostic scope becoming therapeutic, rigid-bronchoscopy conversion or an additional biopsy or drainage procedure.
May be separate
Complications and escalation
Unplanned ICU, ventilation, transfusion, chest drain, re-intervention, readmission or extra nights unless covered.
May be separate
Premium devices and consumables
Airway stents, valves, cryoprobes, catheters and single-use scopes beyond the written specification.
May be separate
Advanced diagnostics
PET-CT, molecular or biomarker testing, special microbiology, expert pathology review and repeat imaging unless listed.
May be separate
Travel and ongoing care
Flights, visa, insurance, lodging, companion, home oxygen, rehabilitation and treatment after return.
May be separate
Complication rescue and external expert review
Chest tube, transfusion, embolization, surgery, ICU, genomic tests and outside pathology review are separate unless written.
Catalog inclusions listed for this pathway: pulmonology consultation and records review; named consultant on camera before travel; scope, anaesthesia and overnight stay as quoted; histology, drain or icu step-down as indicated; discharge summary to your home physician.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- ILD multidisciplinary selection
- Specialist HRCT and pathology review before and after biopsy are part of safe diagnostic use.
- General anaesthesia and airway
- Endotracheal or rigid access and controlled ventilation require theatre-level resources.
- Cryoprobes and gas system
- Probe diameter, number of probes and compatible freezing console add specialized consumables.
- Fluoroscopy and blocker
- Imaging, balloon blocker, guidewire and trained assistants are core safety resources.
- Pathology expertise
- Large-core processing and expert ILD pathology with multidisciplinary review differ from routine histology.
- High-acuity rescue and stay
- Chest drainage, blood products, embolization, surgery, ICU and added nights must be scoped.
- Imaging and physiological testing
- Chest CT or HRCT, PET-CT, spirometry, DLCO, arterial blood gas and echocardiography add lines only when clinically relevant.
- Respiratory reserve and anaesthesia
- Low oxygen, severe airflow limitation, pulmonary hypertension and comorbidity change sedation, monitoring and ICU probability.
- Hospital category and room
- Campus tier, room class, bronchoscopy-suite resources and city shift facility and nursing charges.
- Pathology and follow-up
- Tissue adequacy, microbiology, molecular testing, repeat procedures and review after results alter the complete diagnostic cost.
Cryo-Lung Biopsy: approaches and where they differ
The approach follows the clinical question, imaging target, airway or pleural anatomy, respiratory reserve and available equipment. Each option has different consumables, monitoring and follow-up, so the quotation must name it.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Single-lobe multi-segment cryobiopsy | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | Cores from more than one segment of one lobe aim to represent heterogeneous ILD while limiting pneumothorax exposure. |
| Two-lobe sampling | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | Selected programmes sample separate lobes when radiographic heterogeneity justifies added diagnostic reach and added risk. |
| Different probe diameters and freeze protocols | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | Probe size and freeze time alter core size and bleeding potential; they follow programme protocol rather than a promise of more tissue. |
| Surgical-biopsy alternative pathway | Individual respiratory assessment determines suitability | No separate GAF sheetRelative complexity only | VATS wedge biopsy may provide larger peripheral architecture but requires surgery; no-biopsy multidisciplinary diagnosis may be preferred when procedural risk outweighs added information. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
Diagnostic pulmonology: the subspecialty behind Cryo-Lung Biopsy
Diagnostic pulmonology connects respiratory symptoms and chest imaging to physiological tests, airway inspection and tissue or microbiology sampling. The question being answered determines whether a wash, brushing, forceps biopsy, needle aspiration or parenchymal biopsy is appropriate.
Larger frozen cores preserve architecture but increase risk
Cryobiopsy often supplies broader alveolar and interstitial architecture with less forceps crush, which can help distinguish selected fibrotic or inflammatory patterns. Core dimensions vary with probe, freeze time, location and extraction; larger does not automatically mean diagnostic.
The same tissue volume creates a wider parenchymal defect. Position too close to the pleura increases pneumothorax exposure, while proximity to vessels raises bleeding concern. Fluoroscopy, controlled protocol and immediate blocker inflation are therefore integral, not optional accessories.
The result belongs in multidisciplinary ILD diagnosis
ILD labels are assembled from clinical course, exposures, autoimmune findings, HRCT distribution and pathology. Cryobiopsy is considered only where uncertainty remains and a likely result could alter treatment; it is not a screening test for unexplained breathlessness.
Pathologists need clinical and radiologic context and samples from documented sites. Discordant or unclassifiable tissue may lead to observation, repeat conference or surgical biopsy rather than a forced diagnosis. Patients should know that risk can be incurred without a definitive label.
Risks and side effects of Cryo-Lung Biopsy
Clinically important airway bleeding and pneumothorax are central risks and may require blocker reinflation, repeat bronchoscopy, transfusion, chest tube, ventilation or surgery. Other risks include hypoxaemia, bronchospasm, infection, anaesthetic complications, acute exacerbation of ILD, non-diagnostic tissue and rarely death; no individual rate can be inferred from a programme label.
Ask before travel who pays for unplanned ventilation, ICU, chest drainage, transfusion, repeat biopsy, readmission or a second procedure.
Cryo-Lung Biopsy cost: India vs other medical tourism destinations
India and US values use stored GAF planning ranges; other countries require direct quotations. Compare the same intent, technique, devices, sedation, pathology, ward category and complication terms for transbronchial lung cryobiopsy.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $1,200–$3,500 | Baseline | GAF catalog planning range. The stored figure covers the named procedure only as written. Diagnostic versus therapeutic scope, anaesthesia, devices, pathology and ICU assumptions must be itemized. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Direct quotation required. Compare scope type, biopsy or intervention, anaesthesia, pathology, molecular testing and complication terms rather than a headline package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Direct quotation required. International coordination does not establish tissue adequacy, pathology turnaround, oxygen needs or continuity after return. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Direct quotation required. Pulmonologist, facility, anaesthesia, device, imaging, pathology and follow-up charges may be separate. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Request an estimate tied to the imaging target, technique, device, tissue studies and expected admission. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Private billing varies. Professional billing, eligibility, device scope and postoperative respiratory follow-up require provider confirmation. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, urgent respiratory access, pathology delivery and home handover. |
| United States | $5,000–$14,000 | ≈4× India | Stored self-pay reference. Pulmonologist, anaesthesia, facility, pathology and device charges may be separate; $5,000–$14,000 is a comparison range, not a quotation. |
International comparisons are indicative. Currency, changed findings, an added device or biopsy, pathology scope and respiratory monitoring alter the final amount.
Why do international patients consider India for transbronchial lung cryobiopsy?
Some patients consider India for transbronchial lung cryobiopsy because tertiary respiratory teams, interventional bronchoscopy, pleural services, pathology and respiratory critical care can be coordinated with a national planning range. Price alone is not a clinical reason to travel.
Evaluate clinician, licensure, campus, equipment, anaesthesia, ICU backup, pathology quality, urgent access and home handover. No provider is ranked and no outcome is promised; unstable breathing or suitable local care can make travel inappropriate.
Hospitals and respiratory centres for Cryo-Lung Biopsy in India
Cards follow exact live relationships for Cryo-Lung Biopsy. A general Pulmonology or accreditation label does not establish current acceptance, equipment or outcomes.
Medanta - The Medicity
 JCI Accredited
 NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi
MGM Healthcare, Chennai
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Tamil, Hindi
KIMS Hospitals, Secunderabad
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
2 listed doctors for this pathway
Languages listed: English, Telugu, Hindi
Cryo-Lung Biopsy hospitals in India · Talk to a treatment coordinator
Cryo-Lung Biopsy specialists in India
Profiles appear only when Cryo-Lung Biopsy is an exact current CMS relationship. Verify respiratory subspecialty, availability and campus; placement is not a ranking or outcome claim.

Dr. Bharat Gopal
Pulmonology
27+ years Experience
Diagnostic Bronchoscopy · Therapeutic Bronchoscopy · Severe Asthma Management
English, Hindi
Dr. G. Venkata Lakshmi
Pulmonology
15+ years Experience
Severe Asthma Management · Chronic Obstructive Pulmonary Disease · Obstructive Sleep Apnea
English, Telugu, Hindi
Dr. Deepika Ramachandran
Pulmonology
7+ years Experience
Bronchoscopy · Airway Stenting · Interstitial Lung Disease
English, Tamil, Hindi
Dr. Mahesh Gudelli
Pulmonology
10+ years Experience
Airway Stenting · Bronchiectasis Management · Bronchoscopy
English, Telugu, Hindi
Cryo-Lung Biopsy doctors in India (4 listed) · Get a personalized cost estimate
Cryo-Lung Biopsy cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad use $1,200–$3,500 because no verified city tariff is stored. City overlays add campus geography, transfers, climate, oxygen logistics and follow-up without inventing prices. Cards require an exact current Cryo-Lung Biopsy CMS relationship.
Swipe to compare Indian cities →
Delhi NCR
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–2 nights
No verified Delhi NCR-only tariff for transbronchial lung cryobiopsy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 1 doctor
Mumbai
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–2 nights
No verified Mumbai-only tariff for transbronchial lung cryobiopsy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Bengaluru
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–2 nights
No verified Bengaluru-only tariff for transbronchial lung cryobiopsy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
0 hospitals · consultant match on request
Chennai
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–2 nights
No verified Chennai-only tariff for transbronchial lung cryobiopsy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 1 doctor
Hyderabad
$1,200–$3,500
India planning band — not a city quote
Typical stay 1–2 nights
No verified Hyderabad-only tariff for transbronchial lung cryobiopsy is stored. Use $1,200–$3,500 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
1 hospital · 2 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for transbronchial lung cryobiopsy
What should international patients budget beyond the pulmonology procedure?
International planning starts with records and a named respiratory question. A remote opinion is provisional until examination, image review and anaesthesia assessment confirm the plan.
- Send records
- Provide full hrct image series and multidisciplinary ild conference summary and recent imaging files.
- Remote review
- A named interventional pulmonologist in an experienced cryobiopsy and ILD programme reviews whether transbronchial lung cryobiopsy answers the clinical question.
- Define scope
- Name diagnostic or therapeutic intent, technique, samples, devices and likely stay.
- Itemize quotation
- Clinician, suite, anaesthesia, consumables, pathology, ward and exclusions.
- Plan travel
- Flexible flights, accessible lodging, companion and oxygen or equipment logistics.
- Arrive and reassess
- Examination, oxygen assessment, imaging and pre-anaesthetic review.
- Confirm consent
- Purpose, alternatives, risks, possible escalation and sample limitations.
- Complete procedure
- The consented transbronchial lung cryobiopsy with respiratory monitoring.
- Early recovery
- Airway, oxygen level, bleeding, pain and sedation recovery.
- Review results
- Imaging, cytology, histopathology or microbiology and any next step.
- Clear travel
- Written travel fitness, medicines, oxygen and urgent-contact plan.
- Handover home
- Procedure note, images, pathology and follow-up schedule for the home team.
- Treatment episode$1,200–$3,500
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay1–2 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for transbronchial lung cryobiopsy in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Define the question
Symptoms, diagnosis, imaging target and prior treatment.
Collect records
CT or HRCT, physiology, pathology and admission history.
Identify specialist
Named interventional pulmonologist in an experienced cryobiopsy and ILD programme and exact campus.
Assess reserve
Oxygen, lung function, comorbidity and anaesthesia fitness.
Choose technique
Diagnostic or therapeutic method for the findings.
Compare quotes
Same scope, devices, samples, nights and follow-up.
Plan travel
Flexible travel, accessible lodging, companion and oxygen.
Confirm consent
Purpose, alternatives, risks and possible escalation.
Complete care
Procedure and monitored recovery.
Process samples
Cytology, histopathology, microbiology or molecular tests.
Attend review
Results, oxygen or device plan and next treatment.
Handover home
Procedure record and respiratory follow-up schedule.
Documents to prepare
- Full HRCT image series and multidisciplinary ILD conference summary
- Exposure, autoimmune serology, microbiology and prior pathology records
- Pulmonary function including diffusion capacity, oxygen trend and echocardiography if performed
- Blood count, coagulation, anticoagulants, comorbidities and anaesthetic history
- Recent pulmonology consultation and medication list
- Chest X-ray, CT chest or HRCT reports and image files where available
- Pulmonary function tests including spirometry and DLCO where performed
- Oxygen prescription, CPAP/BiPAP settings and recent admission summaries where relevant
Clinical detail
How the procedure is performed
Under general anaesthesia or deep sedation with a secured airway, a bronchial blocker is positioned and tested. The bronchoscope and cryoprobe advance to the selected segment under fluoroscopy; after confirming distance from pleura, a short controlled freeze captures tissue. Probe and scope are removed together, the blocker is inflated for haemostasis, and several spatially separated cores may be obtained before ultrasound or radiography checks for pneumothorax.
Continuous anaesthesia monitoring accompanies direct measurement of airway bleeding after each sample. Recovery occurs where staff can manage delayed haemorrhage, hypoxaemia and pneumothorax, with serial clinical assessment and imaging. Overnight or higher-acuity observation depends on local protocol and patient reserve.

Main variations
- Single-lobe multi-segment cryobiopsy
- Cores from more than one segment of one lobe aim to represent heterogeneous ILD while limiting pneumothorax exposure.
- Two-lobe sampling
- Selected programmes sample separate lobes when radiographic heterogeneity justifies added diagnostic reach and added risk.
- Different probe diameters and freeze protocols
- Probe size and freeze time alter core size and bleeding potential; they follow programme protocol rather than a promise of more tissue.
- Surgical-biopsy alternative pathway
- VATS wedge biopsy may provide larger peripheral architecture but requires surgery; no-biopsy multidisciplinary diagnosis may be preferred when procedural risk outweighs added information.
Preparation
Selection includes formal ILD conference review of HRCT, exposures, serology and alternatives; pulmonary function, diffusion capacity, oxygen, echocardiography where pulmonary hypertension is suspected, blood count, platelets, coagulation and anticoagulants; and anaesthetic assessment. Target lobes, pleural distance, freeze protocol, blocker, chest-drain and ICU or thoracic-surgical rescue plans are documented.
Clinicians direct fasting, inhalers, anticoagulants, diabetes medicines, antibiotics and oxygen. Active infection or unstable breathing may postpone an elective procedure.
Hospital stay and recovery
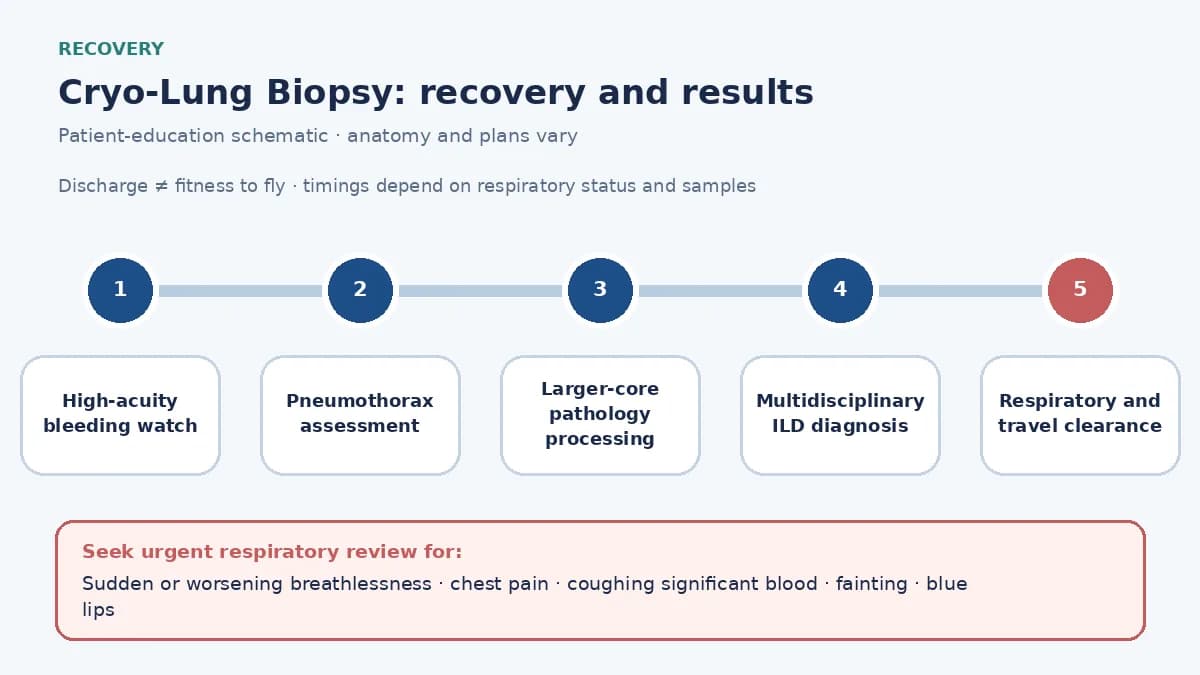
At least overnight monitored admission is common; significant bleeding, pneumothorax, chest drainage or limited reserve can require high-dependency or ICU care. Cough, sore throat and small blood streaks can occur, but vigilance for delayed bleeding and pneumothorax is essential. Pathology undergoes multidisciplinary correlation rather than stand-alone interpretation. Activity and flying are deferred until respiratory status and imaging are stable and the procedural team clears travel.
Follow the oxygen, activity and equipment plan. Seek urgent respiratory help for coughing substantial or increasing blood, sudden or worsening breathlessness, sharp chest pain, fainting, confusion, rapidly falling oxygen or blue lips.
How to compare Cryo-Lung Biopsy quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Who is the named interventional pulmonologist in an experienced cryobiopsy and ILD programme, and at which campus?
- What clinical question will transbronchial lung cryobiopsy answer or treat?
- Is the scope diagnostic, therapeutic or both?
- Which approach is planned, and what might change it?
- Are pulmonologist, anaesthesia and procedure-suite fees included?
- Which imaging and respiratory tests are needed before the procedure?
- Which scopes, needles, probes, stents, valves, drains or catheters are assumed?
- Which cytology, histopathology and microbiology studies are included?
- Is molecular or biomarker testing included when tissue is obtained?
- How many day-care or ward nights are quoted?
- Are oxygen, non-invasive ventilation and ICU escalation covered?
- What is charged if another procedure or repeat sample is needed?
- How are pneumothorax, bleeding, ventilation and readmission billed?
- When will results be ready, and is the results consultation included?
- Which symptoms require urgent review and where?
- When may I work, exercise and fly?
- Who coordinates respiratory follow-up after I return home?
- Has an ILD multidisciplinary team agreed tissue could change management?
- Are fluoroscopy, a tested bronchial blocker and overnight monitoring included?
- What probe, lobes, number of cores and freeze protocol are planned?
- What immediate ICU, interventional-radiology and thoracic-surgery rescue is available?
- Is expert ILD pathology and post-biopsy conference included?
Frequently asked questions
How much does Cryo-Lung Biopsy cost in India?
Cryo-Lung Biopsy is typically planned at $1,200–$3,500 per cryobiopsy admission. This national range is not a quotation; technique, sedation, devices, pathology, ward nights and written terms determine the amount.
What is Cryo-Lung Biopsy?
Transbronchial lung cryobiopsy uses a flexible cryoprobe passed through a bronchoscope into peripheral lung, where rapid cooling freezes parenchyma onto the probe for en-bloc extraction. It yields larger, less-crushed tissue cores than forceps biopsy but carries important bleeding and pneumothorax risks.
When is transbronchial lung cryobiopsy considered?
Cryobiopsy may be considered after multidisciplinary ILD review when HRCT, clinical and laboratory findings remain insufficient and tissue architecture is likely to change management. It requires adequate respiratory reserve and careful exclusion of disproportionate bleeding, pulmonary-hypertension or anaesthetic risk; observation without biopsy or surgical biopsy may be safer or more informative.
What does the transbronchial lung cryobiopsy planning range usually include?
It commonly includes the named respiratory specialist, procedure suite, routine monitoring, sedation or anaesthesia, standard consumables and quoted stay. Imaging, advanced devices, pathology panels and treatment after results may be separate.
What assessment is needed before transbronchial lung cryobiopsy?
Selection includes formal ILD conference review of HRCT, exposures, serology and alternatives; pulmonary function, diffusion capacity, oxygen, echocardiography where pulmonary hypertension is suspected, blood count, platelets, coagulation and anticoagulants; and anaesthetic assessment. Target lobes, pleural distance, freeze protocol, blocker, chest-drain and ICU or thoracic-surgical rescue plans are documented.
How long does transbronchial lung cryobiopsy take?
Often 60–120 minutes, plus anaesthetic setup, repeated haemostasis checks and post-biopsy imaging. Preparation and monitored recovery add time, and pathology or microbiology can extend the overall diagnostic journey.
Is hospitalization needed after transbronchial lung cryobiopsy?
At least overnight monitored admission is common; significant bleeding, pneumothorax, chest drainage or limited reserve can require high-dependency or ICU care. Discharge follows respiratory and clinical criteria, not a package calendar.
What are the important risks of transbronchial lung cryobiopsy?
Clinically important airway bleeding and pneumothorax are central risks and may require blocker reinflation, repeat bronchoscopy, transfusion, chest tube, ventilation or surgery. Other risks include hypoxaemia, bronchospasm, infection, anaesthetic complications, acute exacerbation of ILD, non-diagnostic tissue and rarely death; no individual rate can be inferred from a programme label.
When can an international patient fly after transbronchial lung cryobiopsy?
There is no universal flight day. Activity and flying are deferred until respiratory status and imaging are stable and the procedural team clears travel. The treating team must document travel fitness.
Is cryo-lung biopsy the same as forceps TBLB?
No. A cryoprobe freezes and extracts a larger core with the scope, requiring blocker-based bleeding control and generally more intensive monitoring than small forceps samples.
Why is a bronchial blocker used?
It can temporarily isolate the sampled lobe and limit blood entering the opposite lung while haemostasis is assessed; it does not eliminate bleeding risk.
Does a larger biopsy guarantee an ILD diagnosis?
No. Sampling error, mixed patterns and non-specific injury remain possible, so findings require multidisciplinary correlation.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Transbronchial Lung Biopsy cost in India
$600–$1,800 · stay Outpatient or 1 night
Bronchoscopy cost in India
$400–$1,200 · stay Outpatient or 1 night
Pleural Biopsy cost in India
$600–$1,800 · stay 1–2 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 13 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Cryo-Lung Biopsy cost sheet · All treatment costs in India · Pulmonology costs



