
Last updated: 11 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
TOF Repair in Mumbai is planned against $6,500–$16,000, with 8–16 nights; parent stay expected stored for trip planning. This is not a guaranteed package or a city-specific price.
The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period. Hospital recovery follows hemodynamics, rhythm, feeding and oxygenation; home recovery after sternotomy commonly extends several weeks and lifelong congenital follow-up remains necessary.
- India cost range
- $6,500–$16,000
- Typical starting point
- $6,500
- Typical hospital stay
- 8–16 nights; parent stay expected
- Procedure time
- often 4–7 hours, longer when pulmonary arteries or prior palliation require additional work
- Recovery
- Hospital recovery follows hemodynamics, rhythm, feeding and oxygenation; home recovery after sternotomy commonly extends several weeks and lifelong congenital follow-up remains necessary.
Major cost factors: pulmonary annulus and arteries, coronary anatomy, previous palliation, cyanosis and ventricular function. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: additional anatomy or physiology testing; associated or revised procedures; extended intensive care; later surveillance and medicines; travel and family living costs.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
TOF Repair in Mumbai
Complete repair is generally planned in infancy, but oxygen saturation, cyanotic spells, growth, pulmonary arteries, coronary anatomy and prior shunt or stent influence timing and urgency. Echo defines VSD, outflow obstruction, pulmonary annulus and branches, ventricular function and associated findings; CT or catheterization may clarify pulmonary arteries, collaterals or coronary anatomy in selected cases.
Mumbai and Navi Mumbai are separated accommodation markets. Stay on the same side of the harbour as the confirmed campus, allow for peak-hour transfers, and add monsoon travel slack when relevant. A map distance can understate travel time; early follow-up is easier from lodging close to the treating campus.
The directory must dynamically resolve a clinician and exact campus for TOF repair. Broad cardiac or pediatric labels do not establish that a team offers this operation, has an appropriate ICU bed, or accepts the child.
Send actual imaging and prior operative records before making non-refundable arrangements. A remote opinion may change after examination and repeat testing.
What tof repair typically costs in Mumbai
The national band can move with pulmonary annulus and arteries, coronary anatomy, previous palliation. It should not be divided into an invented daily or city tariff.
Ask the hospital to identify the surgeon or proceduralist, exact campus, planned operation, anesthesia, blood products, ICU and ward nights, routine imaging, exclusions and extra-day policy.
Outside the hospital estimate, budget for travel through Chhatrapati Shivaji Maharaj International Airport, parent lodging close to the campus, local transport, meals, medicines and flexible return flights.
What moves the quote in Mumbai
- Pulmonary annulus and arteries
- Valve-sparing feasibility and branch reconstruction materially change the operation.
- Coronary anatomy
- A coronary crossing the outflow tract may alter surgical access or require a conduit.
- Previous palliation
- A prior shunt or stent adds records, dissection and possible removal.
- Cyanosis and ventricular function
- Physiological condition affects stabilization and ICU support.
Medical travel through Mumbai
Send imaging, clinical notes and the child's current status before booking travel to Mumbai.
Arrive with enough time for pediatric cardiology, surgical and anesthesia review; A map distance can understate travel time; early follow-up is easier from lodging close to the treating campus.
Remain close to the hospital after discharge and travel only when the treating team has assessed fitness to fly.
Hospitals and units listed in Mumbai
Hospital cards for Mumbai should appear only through live GAF relationships to TOF Repair (Tetralogy of Fallot); the article itself names no provider and makes no volume or outcome claim.
Confirm congenital-heart staffing, pediatric anesthesia, postoperative ICU, escalation arrangements and the actual operating campus in writing. General accreditation does not answer those case-specific questions.
TOF Repair doctors in Mumbai · TOF Repair hospitals in Mumbai · TOF Repair cost in India
What Is TOF Repair?
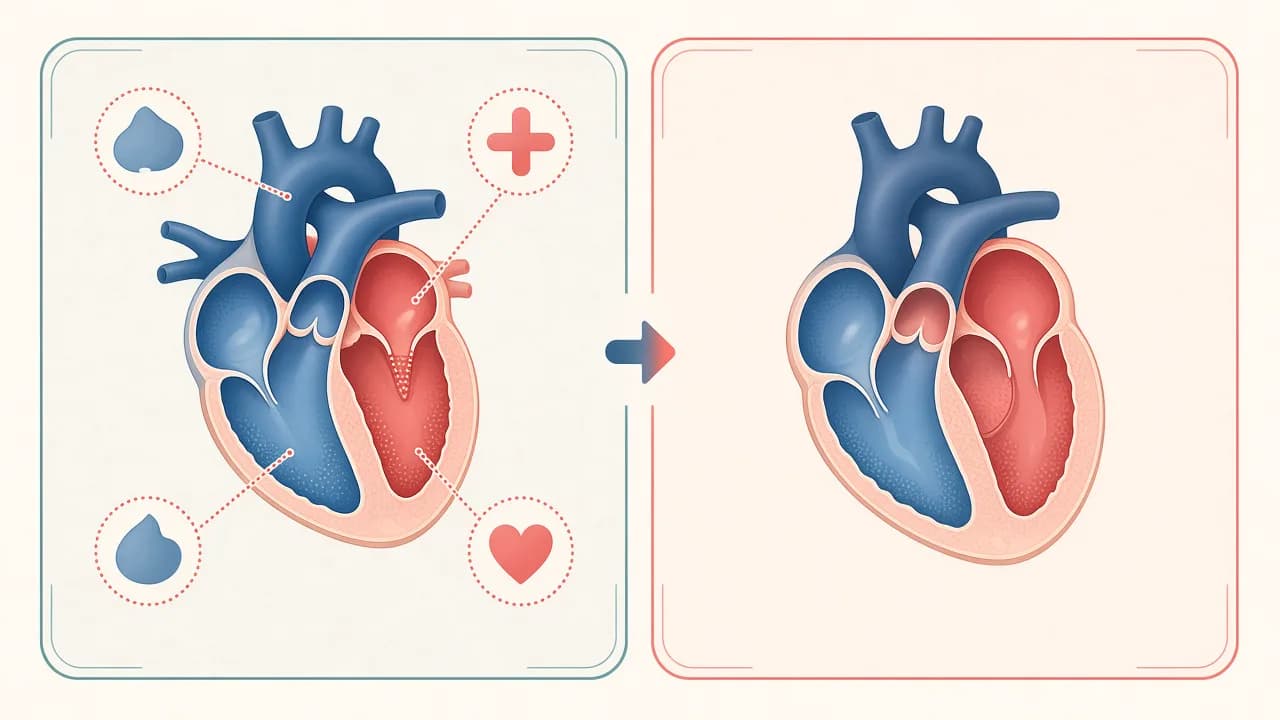
TOF repair addresses a ventricular septal defect and obstruction from the right ventricle to the lungs in tetralogy of Fallot, with the operative plan tailored to pulmonary-valve and artery anatomy.
Complete repair usually closes the VSD and relieves right-ventricular outflow obstruction on bypass; valve-sparing, transannular-patch and conduit strategies are not interchangeable.
When Is TOF Repair Recommended?
Complete repair is generally planned in infancy, but oxygen saturation, cyanotic spells, growth, pulmonary arteries, coronary anatomy and prior shunt or stent influence timing and urgency.
A small or unstable infant, unfavorable pulmonary arteries, important coronary anatomy or another complex feature may lead to palliation or a modified plan before complete repair.
How the operation is performed, recovery and variations →
TOF Repair (Tetralogy of Fallot) cost in India
The $6,500–$16,000 range is a national planning band for TOF repair as quoted. It may include the scheduled procedure, professional fees, operating room or catheter laboratory, anesthesia and a defined ICU and ward allowance. It does not establish what one hospital will charge.
Clinically important cost drivers include pulmonary annulus and arteries, coronary anatomy, previous palliation, cyanosis and ventricular function, associated lesions or collaterals. A change in physiology or planned work is not a cosmetic package upgrade; it may represent a materially different episode of care.
Do not infer separate Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad prices from the national range. Until a verified city figure exists, compare named teams and written inclusions while keeping family travel costs separate.
The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period. Hospital recovery follows hemodynamics, rhythm, feeding and oxygenation; home recovery after sternotomy commonly extends several weeks and lifelong congenital follow-up remains necessary. Return flights and activity dates should remain flexible until the child is examined after treatment.
TOF Repair (Tetralogy of Fallot) cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a surgical estimate, not a dollar amount for each row.
- Congenital-heart review
- Pediatric cardiology and surgical review of imaging, physiology, previous procedures and the indication for TOF repair.
- Preoperative investigations
- The baseline work-up follows the case: Echo defines VSD, outflow obstruction, pulmonary annulus and branches, ventricular function and associated findings; CT or catheterization may clarify pulmonary arteries, collaterals or coronary anatomy in selected cases. Confirm which tests are included and which are conditional.
- Operating room, catheter laboratory and consumables
- The estimate should state the planned approach, bypass or catheter resources, implants or conduits where relevant, and what happens if the plan changes.
- Pediatric anesthesia and perfusion
- Ask whether anesthesia, invasive monitoring, cardiopulmonary bypass and perfusion are included where clinically applicable.
- Cardiac ICU and ward
- The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period. The quote should specify included ICU, ventilation and ward days rather than relying only on 8–16 nights; parent stay expected.
- Medicines, blood products and imaging
- Confirm routine versus high-cost medicines, blood components, laboratory monitoring, echocardiography and discharge prescriptions.
Planning range or quotation?
The $6,500–$16,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a TOF Repair package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Named specialist assessment
A consultation tied to the clinician expected to perform or lead the proposed intervention, where bundled.
Usually included
The written procedure and planned variations
The estimate should use the exact name TOF Repair (Tetralogy of Fallot) and identify associated work rather than say only “heart surgery.”
Usually included
Theater, anesthesia and perfusion
Professional and facility fees for the scheduled episode, with bypass and invasive monitoring stated where relevant.
Usually included
Quoted ICU and ward allowance
Room category and included ventilation, cardiac ICU and ward days; 8–16 nights; parent stay expected is a trip-planning token, not an inclusion promise.
Usually included
Routine inpatient monitoring
Laboratory tests, echocardiography, medicines, dressings and discharge documentation only to the extent written in the quote.
May be charged separately
May be separate
Additional anatomy or physiology testing
Repeat echo, CT, MRI, catheterization, genetic work-up or specialist consultations may be additional when indicated.
May be separate
Associated or revised procedures
Work beyond the documented operative plan, including an unplanned catheter or reoperation, is not automatically bundled.
May be separate
Extended intensive care
Extra ventilation, circulatory support, dialysis, infection care, blood products or additional ICU and ward days generally alter the bill.
May be separate
Later surveillance and medicines
Lifelong congenital-heart surveillance evaluates rhythm, right-ventricular size and function, residual obstruction and pulmonary-valve regurgitation or later intervention. Confirm what occurs after the first postoperative visit and what can be transferred home.
May be separate
Travel and family living costs
Flights, visas, parent accommodation, meals, local transport and schedule changes are normally outside the hospital estimate.
Catalog inclusions listed for this pathway: paediatric cardiac surgery consultation and records review; named surgeon on camera before travel — parent present; theatre, anaesthesia, cardiopulmonary bypass and paediatric cardiac icu as quoted; device or prosthesis as indicated; discharge summary to your home paediatric cardiologist.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Pulmonary annulus and arteries
- Valve-sparing feasibility and branch reconstruction materially change the operation.
- Coronary anatomy
- A coronary crossing the outflow tract may alter surgical access or require a conduit.
- Previous palliation
- A prior shunt or stent adds records, dissection and possible removal.
- Cyanosis and ventricular function
- Physiological condition affects stabilization and ICU support.
- Associated lesions or collaterals
- Additional repair or catheter work broadens the episode.
Approaches related to TOF Repair
Complete repair usually closes the VSD and relieves right-ventricular outflow obstruction on bypass; valve-sparing, transannular-patch and conduit strategies are not interchangeable. These are clinical pathways, not consumer upgrades.
The receiving team should explain why its proposed route fits the child's current anatomy and physiology, and what finding could change that route after arrival.
Swipe to compare surgical approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Valve-sparing complete repair | Selected by anatomy, physiology and stage | No separate GAF sheetRelative complexity only | Relieves obstruction while preserving the pulmonary valve when anatomy permits. |
| Transannular-patch repair | Selected by anatomy, physiology and stage | No separate GAF sheetRelative complexity only | Enlarges a small outflow tract across the annulus, accepting different long-term pulmonary-valve implications. |
| Conduit or staged palliation | Selected by anatomy, physiology and stage | No separate GAF sheetRelative complexity only | A conduit, systemic-to-pulmonary shunt or outflow stent may be discussed for selected anatomy or physiology. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that operation. Other rows describe relative clinical complexity and should not be read as prices.
TOF Repair (Tetralogy of Fallot) cost: India vs other medical tourism destinations
India and United States values come from the stored GAF registry. Other rows are explicitly modelled from relative private-care levels and are not official tariffs or evidence of availability.
International comparisons are easily distorted when operative scope, stage, implants, ICU assumptions and follow-up differ. Obtain like-for-like written estimates after record review.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $6,500–$16,000 | Baseline | GAF catalog planning range. The stored India range is a comparison band; a named congenital-heart team must review the child's records before issuing a case-specific quotation. |
| Turkey | $12,500–$20,500Indicative planning estimate* | ≈1.4× India | Private international-care market. Confirm the exact pediatric program, procedure, ICU assumptions and whether implants or staged care are included. |
| Thailand | $14,500–$25,000Indicative planning estimate* | ≈1.8× India | Private international hospitals. International coordination may be available, but congenital anatomy and pediatric intensive-care support require written confirmation. |
| United Arab Emirates | $25,000–$40,500Indicative planning estimate* | ≈2.9× India | Regional premium private care. Travel may be shorter for Gulf families; specialist, facility and ICU charges may remain separate. |
| Singapore | $31,500–$54,000Indicative planning estimate* | ≈3.8× India | High-cost specialist private care. Ask for an international self-pay estimate tied to the exact congenital diagnosis rather than a general cardiac package. |
| Germany | $28,000–$50,500Indicative planning estimate* | ≈3.5× India | European congenital-heart care. International access, professional billing and post-discharge arrangements vary by center and should be established before travel. |
| United Kingdom | $25,000–$45,000Indicative planning estimate* | ≈3.1× India | Private self-pay for many visitors. Overseas families should verify eligibility, the treating unit and whether investigations and follow-up are separately charged. |
| United States | $50,000–$140,000 | ≈8.4× India | Stored self-pay reference. Facility, surgeon, anesthesia, imaging, ICU and follow-up may be billed by different entities; $50,000–$140,000 is a comparison range, not one bundled quote. |
*Figures other than India and the United States are modelled planning estimates scaled from the India catalog band, not hospital quotations. All figures are planning information. Currency, anatomy, urgency, clinical course, hospital terms and length of stay can change the final amount; no row predicts outcomes.
Why do international patients consider India for TOF repair?
Some international families evaluate India for access to a named pediatric congenital-heart team and a self-pay planning band below typical United States figures. Cost alone is not a reason to move a child.
The key questions are clinical acceptance, appropriate pediatric anesthesia and intensive care, the proposed team's relevance to the anatomy, and continuity after return. These require direct written confirmation.
No hospital or clinician is described as best. An unstable newborn or child may be unsafe to fly, and established funded care near home may be more appropriate.
Hospitals for TOF Repair in Mumbai
Hospital cards should follow live entity relationships, not names embedded in editorial copy. Accreditation or a general cardiac label does not prove current pediatric congenital capability, ICU availability, case acceptance or outcomes.
Campuses for this pathway are being confirmed. Ask the desk which houses currently quote it.
TOF Repair Doctors in Mumbai
Profiles should be pulled dynamically only when TOF Repair (Tetralogy of Fallot) appears in the clinician's current procedure relationships. Verify role, case relevance, availability and campus. Placement is not a ranking, and this article adds no experience or outcome claim.
Named consultants for this pathway are being matched. Request a dossier and we will advise which campuses can quote it.
TOF Repair cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad retain $6,500–$16,000 until verified city-level data is stored. Their overlays focus on genuinely different airport, geography and family-stay logistics.
Clinician and hospital cards must resolve dynamically from current data. This module names no provider, makes no capability assumption and offers no ranking.
Swipe to compare Indian cities →
Delhi NCR
$6,500–$16,000
India planning band — not a city quote
Typical stay 8–16 nights; parent stay expected
No verified Delhi NCR-only tariff is stored. Use $6,500–$16,000 as the national planning band until a named hospital supplies an itemized case estimate.
6 hospitals · 10 doctors
Mumbai
$6,500–$16,000
India planning band — not a city quote
Typical stay 8–16 nights; parent stay expected
No verified Mumbai-only tariff is stored. Use $6,500–$16,000 as the national planning band until a named hospital supplies an itemized case estimate.
0 hospitals · consultant match on request
Bengaluru
$6,500–$16,000
India planning band — not a city quote
Typical stay 8–16 nights; parent stay expected
No verified Bengaluru-only tariff is stored. Use $6,500–$16,000 as the national planning band until a named hospital supplies an itemized case estimate.
0 hospitals · consultant match on request
Chennai
$6,500–$16,000
India planning band — not a city quote
Typical stay 8–16 nights; parent stay expected
No verified Chennai-only tariff is stored. Use $6,500–$16,000 as the national planning band until a named hospital supplies an itemized case estimate.
1 hospital · 3 doctors
Hyderabad
$6,500–$16,000
India planning band — not a city quote
Typical stay 8–16 nights; parent stay expected
No verified Hyderabad-only tariff is stored. Use $6,500–$16,000 as the national planning band until a named hospital supplies an itemized case estimate.
2 hospitals · 3 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for TOF repair
What should international patients budget beyond the surgery?
A complete TOF repair budget includes much more than the $6,500–$16,000 hospital planning band. Add remote review, tests not bundled, parent travel, lodging, local transport, medicines and contingency for extra nights.
Travel should follow a written clinical acceptance and itemized estimate. A visa letter or directory card is not medical clearance.
- Records and stability review
- Share imaging, current observations, symptoms, growth or feeding, medicines, prior procedures and the referring clinician's question.
- Multidisciplinary planning
- Pediatric cardiology, congenital surgery, anesthesia and intensive-care teams clarify indication, timing, approach and whether commercial travel is appropriate.
- Itemized estimate and logistics
- Match the exact procedure to included tests, implants, bypass, ICU and ward days, exclusions, escalation rates and parent accommodation.
- Arrival and reassessment
- Allow time for examination, repeat imaging, blood tests and anesthesia review; consent should include alternatives and child-specific uncertainty.
- Procedure and monitored recovery
- Complete repair usually closes the VSD and relieves right-ventricular outflow obstruction on bypass; valve-sparing, transannular-patch and conduit strategies are not interchangeable. The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period.
- Discharge, nearby review and handover
- Hospital recovery follows hemodynamics, rhythm, feeding and oxygenation; home recovery after sternotomy commonly extends several weeks and lifelong congenital follow-up remains necessary. Travel only after review and carry the operative note, imaging, medicine plan and follow-up schedule.
- Treatment episode$6,500–$16,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay8–16 nights; parent stay expected typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for TOF repair in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Send complete records
Provide actual imaging, reports, current clinical observations, medicines and all prior catheter or operative notes.
Confirm clinical acceptance
A named congenital-heart team reviews diagnosis, urgency, stage, travel safety and the likely intervention.
Hold a remote family discussion
Ask why treatment is indicated now, what alternatives exist, what remains uncertain and who will lead care.
Compare itemized quotations
Use the same operative scope and ICU assumptions; do not compare a partial estimate with a comprehensive episode.
Plan flexible travel
Obtain required documents, refundable flights and lodging near the exact campus, with contingency for a longer stay.
Repeat assessment after arrival
The child is examined and undergoes indicated imaging, laboratory and anesthesia review before final consent.
Treatment and pediatric cardiac ICU
Care follows the agreed approach, with escalation according to the child's condition rather than package limits.
Step down and prepare discharge
Parents learn medicine, feeding, wound, activity and warning-sign instructions and receive written records.
Complete local review
Remain nearby until the team reviews recovery and explicitly discusses fitness for travel.
Continue care at home
Transfer records to the child's local clinician. Lifelong congenital-heart surveillance evaluates rhythm, right-ventricular size and function, residual obstruction and pulmonary-valve regurgitation or later intervention.

Documents to prepare
- Oxygen-saturation trend and records of cyanotic spells
- Details of any prior shunt, RVOT stent or catheter intervention
- Most recent echocardiogram report and complete image loops or DICOM files
- ECG and any rhythm-monitor, catheterization, CT or MRI records
- Current medication list, allergies, vaccination history and recent laboratory results
- Growth, feeding, oxygen-saturation and symptom history
- All prior cardiac operative notes, discharge summaries and implant details
- Passport and guardian documentation required for travel and consent
Clinical detail
How the operation is performed
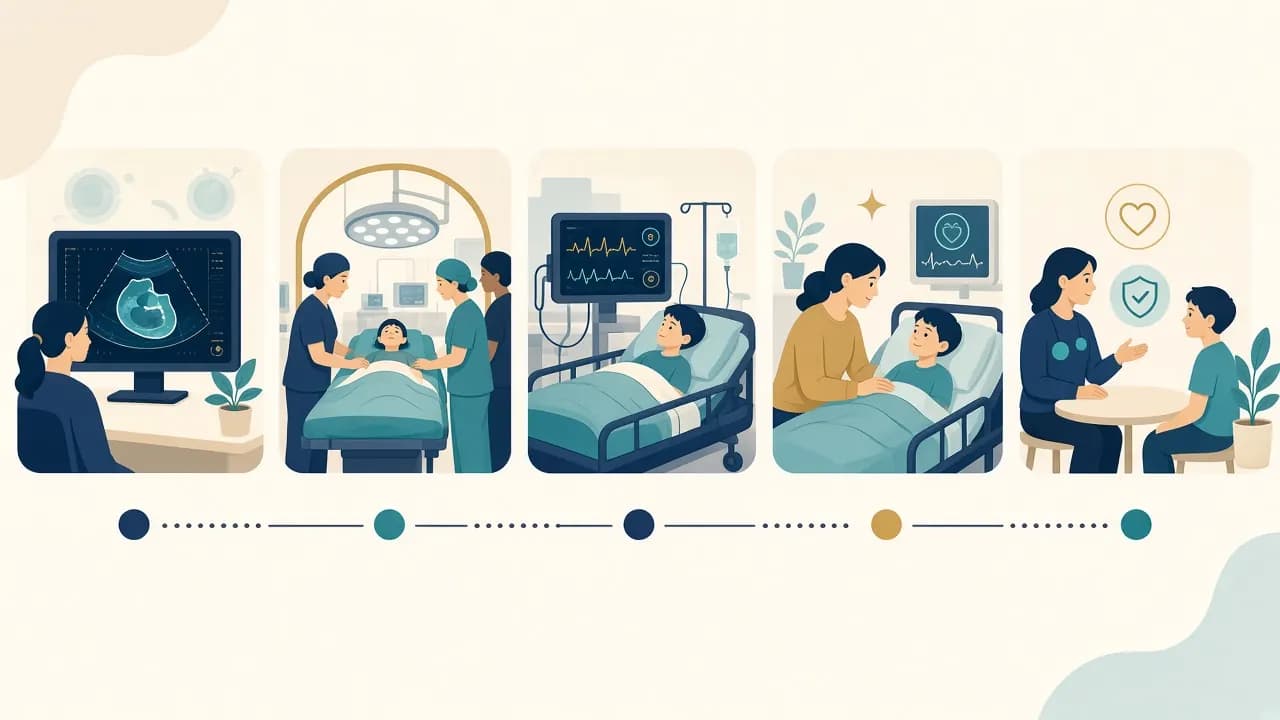
Complete repair usually closes the VSD and relieves right-ventricular outflow obstruction on bypass; valve-sparing, transannular-patch and conduit strategies are not interchangeable.
The listed procedural forms are Valve-sparing complete repair, Transannular-patch repair, Conduit or staged palliation. The sequence, incision, bypass strategy, implants and associated repairs depend on the child's anatomy.
The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period. Monitoring commonly includes circulation, oxygenation, rhythm, urine output, bleeding, neurological status, feeding and imaging as relevant.
Main variations
- Valve-sparing complete repair
- Relieves obstruction while preserving the pulmonary valve when anatomy permits.
- Transannular-patch repair
- Enlarges a small outflow tract across the annulus, accepting different long-term pulmonary-valve implications.
- Conduit or staged palliation
- A conduit, systemic-to-pulmonary shunt or outflow stent may be discussed for selected anatomy or physiology.
Preparation
Echo defines VSD, outflow obstruction, pulmonary annulus and branches, ventricular function and associated findings; CT or catheterization may clarify pulmonary arteries, collaterals or coronary anatomy in selected cases. Send complete records rather than screenshots or a one-line report.
The receiving team sets fasting and medication instructions. Report fever, respiratory symptoms, infection, feeding deterioration or a change in oxygen saturation promptly; these may alter timing.
Hospital stay and recovery
The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period. Hospital recovery follows hemodynamics, rhythm, feeding and oxygenation; home recovery after sternotomy commonly extends several weeks and lifelong congenital follow-up remains necessary.
The catalog's 8–16 nights; parent stay expected is for broad planning, not a discharge promise. Drainage, oxygen need, feeding, wound healing, rhythm and repeat imaging can affect the actual stay.
Child-specific consent may address low cardiac output, arrhythmia, residual VSD or obstruction, pulmonary regurgitation, branch pulmonary-artery issues, reintervention, neurological events, bleeding and infection.
Lifelong congenital-heart surveillance evaluates rhythm, right-ventricular size and function, residual obstruction and pulmonary-valve regurgitation or later intervention. Families need a written handover, emergency contacts and a local pediatric cardiology plan.
Seek urgent clinical help for breathing difficulty, blue or unusually pale color, fainting, persistent fever, wound concerns, poor feeding, marked lethargy, reduced urine, new swelling or any warning sign specified at discharge.
How to compare TOF Repair quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is TOF repair recommended now, and what alternatives were considered?
- Which anatomy, physiology or previous-stage finding drives the plan?
- Who will perform the procedure, and at which exact campus?
- Does the quotation use the exact treatment name and list associated work?
- Which investigations must be repeated after arrival, and are they included?
- Are pediatric anesthesia, perfusion and blood products included where relevant?
- How many ventilation, cardiac ICU and ward days are included?
- Which implants, patches, conduits, devices or special medicines are assumed?
- What finding could change the approach or require an additional procedure?
- How are extra ICU days, reintervention, infection care or other complications billed?
- What room category is quoted, and can a parent remain nearby?
- Which discharge imaging, medicines and first follow-up are included?
- What warning signs and local emergency plan should the family use?
- When will the team assess fitness to fly, and what follow-up is needed at home?
- Is the plan valve-sparing, transannular patch or conduit, and what could change it?
- Does the estimate include work on branch pulmonary arteries or prior shunt removal?
Frequently asked questions
How much does TOF repair cost in Mumbai?
Use $6,500–$16,000 as the stored India planning range. No verified Mumbai-only price is stored; the final amount follows record review and an itemized hospital letter.
Which Mumbai doctors perform TOF repair?
Only profiles dynamically matched to this exact procedure should be shown. Verify role, current appointment, operating campus and experience relevant to the child's anatomy; placement is not a ranking.
Which hospital in Mumbai should a family choose?
There is no universal best hospital. Compare the named team, pediatric ICU and anesthesia plan, exact campus, quote boundaries and continuity after discharge.
Where should a family stay in Mumbai?
Mumbai and Navi Mumbai are separated accommodation markets. Stay on the same side of the harbour as the confirmed campus, allow for peak-hour transfers, and add monsoon travel slack when relevant. Keep bookings flexible until the admission and early review dates are confirmed.
When can the child fly home?
There is no universal flight date. The treating team must review oxygenation, feeding, wounds, rhythm, imaging and any drains or medicines before clearing travel.
How much does TOF repair cost in India?
TOF Repair is typically planned at $6,500–$16,000. This stored range is not a quote; anatomy, urgency, operative scope, ICU support and hospital terms determine the final amount.
What is TOF repair?
TOF repair addresses a ventricular septal defect and obstruction from the right ventricle to the lungs in tetralogy of Fallot, with the operative plan tailored to pulmonary-valve and artery anatomy.
When is TOF repair considered?
Complete repair is generally planned in infancy, but oxygen saturation, cyanotic spells, growth, pulmonary arteries, coronary anatomy and prior shunt or stent influence timing and urgency.
Does every child with this diagnosis need the same procedure?
A small or unstable infant, unfavorable pulmonary arteries, important coronary anatomy or another complex feature may lead to palliation or a modified plan before complete repair. Timing and approach require individualized congenital-heart review.
What tests are needed before treatment?
Echo defines VSD, outflow obstruction, pulmonary annulus and branches, ventricular function and associated findings; CT or catheterization may clarify pulmonary arteries, collaterals or coronary anatomy in selected cases.
What approaches may be discussed?
Complete repair usually closes the VSD and relieves right-ventricular outflow obstruction on bypass; valve-sparing, transannular-patch and conduit strategies are not interchangeable. Relevant forms include Valve-sparing complete repair, Transannular-patch repair, Conduit or staged palliation; they are selected clinically, not by package price.
How long does TOF repair take?
often 4–7 hours, longer when pulmonary arteries or prior palliation require additional work This is an orientation only; associated work and the child's condition can extend the episode.
Will the child need pediatric cardiac intensive care?
The ICU watches right-ventricular function, oxygenation, rhythm, low cardiac output, bleeding and ventilation; some children need a longer support period.
How long is recovery?
Hospital recovery follows hemodynamics, rhythm, feeding and oxygenation; home recovery after sternotomy commonly extends several weeks and lifelong congenital follow-up remains necessary. The stored stay is 8–16 nights; parent stay expected, but discharge and travel dates remain individualized.
What can make the quotation change?
Important drivers include pulmonary annulus and arteries, coronary anatomy, previous palliation, cyanosis and ventricular function, associated lesions or collaterals. Ask for each change in writing.
Are complications and extra ICU days included?
Only if the itemized estimate says so. Ask how ventilation, circulatory support, blood products, infection care, reintervention and days beyond the allowance are billed.
How should an international family choose a team?
Verify the proposed clinician's role, relevance to the child's anatomy and stage, exact campus, pediatric ICU and anesthesia support, communication and handover plan. Directory placement is not a ranking.
Can the child fly soon after treatment?
There is no universal safe date. The treating team must assess circulation, oxygenation, feeding, wounds, rhythm and imaging before clearing travel.
What follow-up is required?
Lifelong congenital-heart surveillance evaluates rhythm, right-ventricular size and function, residual obstruction and pulmonary-valve regurgitation or later intervention.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
VSD Closure (Ventricular Septal Defect) cost in India
$4,500–$11,000 · stay 6–12 nights; parent stay expected
PDA Closure (Patent Ductus Arteriosus) cost in India
$3,500–$8,500 · stay 3–8 nights; parent stay expected
Glenn Procedure cost in India
$8,000–$18,000 · stay 8–16 nights; parent stay expected
Coarctation Repair cost in India
$6,000–$15,000 · stay 6–14 nights; parent stay expected
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 11 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
TOF Repair (Tetralogy of Fallot) cost sheet · All treatment costs in India · Pediatric Cardiac Surgery costs



