
Last updated: 12 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
TAVR/TAVI (Transcatheter Aortic Valve Replacement) in Mumbai is planned against $18,000–$42,000, with 3–7 nights typical stored only for broad trip planning. Neither token is a city tariff, admission promise or final quotation.
In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction. Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function.
- India cost range
- $18,000–$42,000
- Typical starting point
- $18,000
- Typical hospital stay
- 3–7 nights typical
- Procedure time
- often about 1–3 hours, with planning and monitored recovery outside procedure time
- Recovery
- After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness.
Major cost factors: valve platform and size, transfemoral versus alternative access, coronary and annular anatomy, pacemaker and vascular risk. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: alternative-access conversion or emergency surgery; permanent pacemaker; coronary or peripheral intervention; major bleeding, stroke or kidney support; long-term antithrombotic therapy and echo.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
TAVR/TAVI (Transcatheter Aortic Valve Replacement) in Mumbai
It may be considered for severe symptomatic aortic stenosis and selected other guideline-supported settings after a multidisciplinary Heart Team weighs age, life expectancy, surgical risk, anatomy, durability and patient goals. Echo confirms valve severity; ECG-gated TAVR CT sizes the annulus, assesses calcium, coronary heights, root and iliofemoral access. Coronary, renal, rhythm, frailty, dental or infection and surgical assessments complete Heart Team review.
Mumbai and Navi Mumbai are not interchangeable bases. Peak traffic, harbour crossings and monsoon disruption can delay pre-admission testing or an urgent return after discharge. A long-haul patient should have a rest and reassessment interval before an elective procedure.
Wet pavements, stairs and long vehicle journeys are poor early-mobility plans after chest surgery. Confirm where wound review, anticoagulation testing and rehabilitation will occur. Stay on the same side of the harbour as the confirmed hospital and keep the return booking changeable until the postoperative review.
Doctor and hospital cards in Mumbai must come only from live catalog relationships that exactly tag TAVR/TAVI (Transcatheter Aortic Valve Replacement). When that mapping is absent, the cards must remain empty: do not borrow a generic cardiac entity. An empty area is a catalog gap, not a ranking, outcome or capability statement.
Send complete imaging and prior operative records before paying for non-refundable travel. The final plan may change after examination, repeat tests or multidisciplinary review.
What tavr/tavi (transcatheter aortic valve replacement) typically costs in Mumbai
The estimate changes with valve platform and size, transfemoral versus alternative access, coronary and annular anatomy, pacemaker and vascular risk. These are clinical differences, not premium upgrades.
Ask the hospital to identify the Structural Heart Team specialist, exact campus, operation or device, anaesthesia, perfusion where relevant, blood products, ICU allowance, exclusions and extra-day policy.
Budget separately for travel through Chhatrapati Shivaji Maharaj International Airport, stay on the same side of the harbour as the confirmed hospital and keep the return booking changeable until the postoperative review. Keep flights flexible until fitness to travel is documented.
What moves the quote in Mumbai
- Valve platform and size
- Implant selection follows CT anatomy, not a generic device package.
- Transfemoral versus alternative access
- Access route changes team, facility and recovery needs.
- Coronary and annular anatomy
- Low coronaries, heavy calcium and prior valves can require protection strategies.
- Pacemaker and vascular risk
- Conduction observation and vascular intervention may extend admission.
Medical travel through Mumbai
Send current echo, angiography or CT and all prior cardiac records before booking travel to Mumbai.
Obtain written acceptance from a named Structural Heart Team specialist and allow for repeat assessment after arrival. Mumbai and Navi Mumbai are not interchangeable bases. Peak traffic, harbour crossings and monsoon disruption can delay pre-admission testing or an urgent return after discharge.
After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness. Stay on the same side of the harbour as the confirmed hospital and keep the return booking changeable until the postoperative review. Travel home only after wound, rhythm, oxygenation and mobility review.
Hospitals and units listed in Mumbai
Doctor and hospital cards in Mumbai must come only from live catalog relationships that exactly tag TAVR/TAVI (Transcatheter Aortic Valve Replacement). When that mapping is absent, the cards must remain empty: do not borrow a generic cardiac entity. An empty area is a catalog gap, not a ranking, outcome or capability statement.
Confirm the exact operating campus, named lead clinician, cardiac anaesthesia, perfusion or catheter support as applicable, ICU escalation and follow-up in writing. General accreditation does not establish procedure-specific availability or outcomes.
TAVR/TAVI (Transcatheter Aortic Valve Replacement) doctors in Mumbai · TAVR/TAVI (Transcatheter Aortic Valve Replacement) hospitals in Mumbai · TAVR/TAVI (Transcatheter Aortic Valve Replacement) cost in India
What Is TAVR/TAVI (Transcatheter Aortic Valve Replacement)?
TAVR, also called TAVI, treats selected severe aortic stenosis by delivering a collapsible tissue valve through a catheter, most often from the femoral artery, without open-heart valve replacement.
In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction.
TAVR is not open surgery and is not suitable for every valve or patient. Active infection, unsuitable annulus or access, need for other cardiac surgery, unfavorable coronary or root anatomy, or durability priorities may favor surgery or another plan.

When Is TAVR/TAVI (Transcatheter Aortic Valve Replacement) Considered?
It may be considered for severe symptomatic aortic stenosis and selected other guideline-supported settings after a multidisciplinary Heart Team weighs age, life expectancy, surgical risk, anatomy, durability and patient goals.
Echo confirms valve severity; ECG-gated TAVR CT sizes the annulus, assesses calcium, coronary heights, root and iliofemoral access. Coronary, renal, rhythm, frailty, dental or infection and surgical assessments complete Heart Team review.
How treatment is given, monitored and adapted →
TAVR/TAVI (Transcatheter Aortic Valve Replacement) cost in India
The $18,000–$42,000 value is the national catalog planning range for TAVR or TAVI. It applies only to the procedure name and assumptions written in a hospital letter; it is not a guaranteed package or a tariff for any provider or city.
Important drivers are valve platform and size, transfemoral versus alternative access, coronary and annular anatomy, pacemaker and vascular risk, renal function and contrast planning. An added graft, prosthesis, reconstruction, prolonged ICU stay or changed access can describe a different clinical episode.
Compare itemized quotations using the same diagnosis and procedure scope. Never derive separate Delhi NCR, Mumbai, Bengaluru, Chennai or Hyderabad prices from this national token, and keep flights, lodging, rehabilitation and care after return outside the comparison.
Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function. After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness. International travel should remain flexible until the treating team documents fitness.
TAVR/TAVI (Transcatheter Aortic Valve Replacement) cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a treatment estimate, not a dollar amount for each row.
- Multidisciplinary Heart Team review
- Documented catheter-versus-surgery decision.
- TAVR planning imaging
- CT and other studies only when expressly listed.
- One named transcatheter valve
- Platform, size assumptions and supply terms.
- Catheter or hybrid room and anaesthesia
- Imaging, access and closure resources as written.
- Quoted monitored stay and early echo
- Rhythm and valve checks within defined limits.
Planning range or quotation?
The $18,000–$42,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a TAVR/TAVI (Transcatheter Aortic Valve Replacement) package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a cardiac procedure estimate for this treatment. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Multidisciplinary Heart Team review
Documented catheter-versus-surgery decision.
Usually included
TAVR planning imaging
CT and other studies only when expressly listed.
Usually included
One named transcatheter valve
Platform, size assumptions and supply terms.
Usually included
Catheter or hybrid room and anaesthesia
Imaging, access and closure resources as written.
Usually included
Quoted monitored stay and early echo
Rhythm and valve checks within defined limits.
May be charged separately
May be separate
Alternative-access conversion or emergency surgery
Additional rescue resources unless stated.
May be separate
Permanent pacemaker
A separate implant and admission unless included.
May be separate
Coronary or peripheral intervention
PCI, protection stents or vascular repair outside scope.
May be separate
Major bleeding, stroke or kidney support
Complication care beyond written terms.
May be separate
Long-term antithrombotic therapy and echo
Medicines and surveillance after the included period.
Catalog inclusions listed for this pathway: cardiac surgery consultation and records review; named surgeon on camera before travel; theatre, anaesthesia, cardiopulmonary bypass and cardiac icu as quoted; device or prosthesis as indicated; discharge summary to your home cardiologist.
What can increase the cost?
These are the drivers that actually move a bill for this procedure, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Valve platform and size
- Implant selection follows CT anatomy, not a generic device package.
- Transfemoral versus alternative access
- Access route changes team, facility and recovery needs.
- Coronary and annular anatomy
- Low coronaries, heavy calcium and prior valves can require protection strategies.
- Pacemaker and vascular risk
- Conduction observation and vascular intervention may extend admission.
- Renal function and contrast planning
- Kidney protection and added imaging influence the episode.
Approaches related to TAVR/TAVI (Transcatheter Aortic Valve Replacement)
In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction. The options below are clinical strategies, not consumer upgrades.
A named Structural Heart Team specialist should explain why the proposed approach fits, what alternatives were considered and what finding could change the plan.
Swipe to compare treatment approaches →
| Approach | Relative complexity | GAF planning range | Notes |
|---|---|---|---|
| Transfemoral TAVR | Selected from anatomy, disease, fitness and goals | No separate GAF sheetRelative complexity only | Preferred when iliofemoral access is suitable; closure devices and vascular backup are part of planning. |
| Alternative-access TAVR | Selected from anatomy, disease, fitness and goals | No separate GAF sheetRelative complexity only | Used selectively when femoral access is unsuitable; route and invasiveness vary and must be explicit. |
| Surgical AVR instead | Selected from anatomy, disease, fitness and goals | No separate GAF sheetRelative complexity only | May be more appropriate for younger patients, unfavorable anatomy, bicuspid or aortic disease, endocarditis or needed CABG/other surgery. |
Planning ranges appear only where GAF Healthcare already publishes a cost sheet for that procedure. Other rows describe relative clinical complexity and should not be read as prices.
Risks and recovery after TAVR/TAVI (Transcatheter Aortic Valve Replacement)
Risks include death, stroke, major vascular injury or bleeding, annular rupture, coronary obstruction, paravalvular leak, valve malposition or embolization, kidney injury, infection and new conduction block requiring a permanent pacemaker.
This is not an exhaustive consent list and assigns no probability. Risk depends on current anatomy, urgency, prior operations, frailty, other organs and the actual technique.
After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness. No article can promise technical success, survival, a complication-free course or a fixed return date.
TAVR/TAVI (Transcatheter Aortic Valve Replacement) cost: India vs other medical tourism destinations
India and United States values use stored GAF catalog ranges. Other country rows are explicitly modelled relative private-care bands, not official tariffs, provider quotes or evidence that a program will accept the case.
A valid comparison holds procedure scope, implant or graft assumptions, ICU coverage and follow-up constant. Currency and billing structures can still make rows unlike.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $18,000–$42,000 | Baseline | GAF catalog planning range. The stored India value is a national planning band. A named Heart Team must review the diagnosis, anatomy, fitness and proposed procedure before a hospital can issue an itemized estimate. |
| Turkey | $33,000–$54,000Indicative planning estimate* | ≈1.4× India | Private international-care market. Compare the exact operation, prosthesis or device, intensive-care allowance, complications and follow-up rather than headline cardiac packages. |
| Thailand | $39,000–$66,000Indicative planning estimate* | ≈1.8× India | Private international hospitals. International coordination does not establish candidacy, implant availability, surgeon responsibility or a safe handover after return. |
| United Arab Emirates | $66,000–$108,000Indicative planning estimate* | ≈2.9× India | Regional premium private care. Travel may be shorter for some families, while professional, implant, ICU and rehabilitation charges may remain separate. |
| Singapore | $84,000–$144,000Indicative planning estimate* | ≈3.8× India | High-cost specialist private care. Request an international self-pay estimate tied to current imaging and the exact cardiac pathway, not a general surgery bundle. |
| Germany | $75,000–$135,000Indicative planning estimate* | ≈3.5× India | European specialist cardiac care. International acceptance, professional billing, implant rules and postoperative arrangements vary and must be established before travel. |
| United Kingdom | $66,000–$120,000Indicative planning estimate* | ≈3.1× India | Private self-pay for many visitors. Overseas patients should verify clinical acceptance, quote boundaries and who provides anticoagulation, wound and cardiac follow-up. |
| United States | $50,000–$150,000 | ≈3.3× India | Stored self-pay reference. Hospital, surgeon, anaesthesia, implant, imaging and rehabilitation bills may be separate; $50,000–$150,000 is a stored comparison range, not one guaranteed quotation. |
*Figures other than India and the United States are modelled planning estimates scaled from the India catalog band, not hospital quotations. All values are planning information. Anatomy, urgency, implants, clinical course, complications, currency and length of stay can change the final bill; no country row predicts availability, safety or outcome.
Why do international patients consider India for TAVR or TAVI?
Some international patients compare India for access to a named Structural Heart Team specialist and a national self-pay planning range below typical United States figures. Price alone is not a clinical reason to travel.
Responsible selection requires case acceptance, an exact procedure and implant plan, critical-care support, an itemized estimate, a safe companion and continuity after return. These points need direct confirmation.
Emergency disease, clinical instability, inability to sustain follow-up or appropriate funded care near home may make international travel unsuitable. This article names no best provider and makes no outcome claim.
Hospitals for TAVR/TAVI (Transcatheter Aortic Valve Replacement) in Mumbai
Hospital cards must follow exact live procedure relationships. General cardiac branding or accreditation does not prove current program capability, implant stock, critical-care availability, volume or outcomes; absent mappings stay empty.
Wockhardt Hospital, Mumbai
 JCI Accredited
 NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
2 listed doctors for this pathway
Languages listed: English, Hindi, Marathi
Gleneagles Hospital, Mumbai
- JCI Accredited
- NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi, Marathi
KIMS Hospitals, Thane
- JCI Accredited
- NABH Accredited
- NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Hindi, Marathi
TAVR/TAVI (Transcatheter Aortic Valve Replacement) hospitals in Mumbai · Talk to a treatment coordinator
TAVR/TAVI (Transcatheter Aortic Valve Replacement) specialists in Mumbai
Profiles must be rendered only when a live relationship exactly maps the clinician to TAVR/TAVI (Transcatheter Aortic Valve Replacement). If no exact mapping exists, leave cards empty rather than borrowing a generic cardiologist or surgeon. Verify current role, responsibility, campus and availability; placement is not a ranking, volume or outcome claim.

Dr. Dipak Patil
Cardiology
12+ years Experience
Coronary Angiography · Coronary Angioplasty & Stenting · Coronary Artery Disease Management
English, Hindi, Marathi
Dr. Milind Phadke
Cardiology
14+ years Experience
Coronary Angioplasty & Stenting · Coronary Angiography · TAVI / TAVR
English, Hindi, Marathi
Dr. Nazir Juwale
Cardiology
42+ years Experience
Coronary Angiography · Coronary Angioplasty & Stenting · Diagnostic Cardiac Catheterization
English, Hindi, Marathi
Dr. Parin Sangoi
Cardiology
11+ years Experience
TAVI / TAVR · MitraClip Procedure · Coronary Angioplasty & Stenting
English, Hindi, Marathi
TAVR/TAVI (Transcatheter Aortic Valve Replacement) doctors in Mumbai (4 listed) · Get a personalized cost estimate
TAVR/TAVI (Transcatheter Aortic Valve Replacement) cost by city in India
Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad use $18,000–$42,000 because the catalog contains no verified city tariff for these procedures. The overlays change airport, commute, climate, lodging and recovery logistics without inventing local prices.
Doctor and hospital cards must resolve only from exact live procedure relationships. Where mappings are absent they remain empty; this article supplies no generic substitutes, ranking, volume, capability or outcome claim.
Swipe to compare Indian cities →
Delhi NCR
$18,000–$42,000
India planning band — not a city quote
Typical stay 3–7 nights typical
No verified Delhi NCR-only tariff is stored for TAVR or TAVI. Use $18,000–$42,000 as the national planning range until a named hospital issues an itemized estimate; this is not a city price.
8 hospitals · 28 doctors
Mumbai
$18,000–$42,000
India planning band — not a city quote
Typical stay 3–7 nights typical
No verified Mumbai-only tariff is stored for TAVR or TAVI. Use $18,000–$42,000 as the national planning range until a named hospital issues an itemized estimate; this is not a city price.
3 hospitals · 4 doctors
Bengaluru
$18,000–$42,000
India planning band — not a city quote
Typical stay 3–7 nights typical
No verified Bengaluru-only tariff is stored for TAVR or TAVI. Use $18,000–$42,000 as the national planning range until a named hospital issues an itemized estimate; this is not a city price.
1 hospital · 1 doctor
Chennai
$18,000–$42,000
India planning band — not a city quote
Typical stay 3–7 nights typical
No verified Chennai-only tariff is stored for TAVR or TAVI. Use $18,000–$42,000 as the national planning range until a named hospital issues an itemized estimate; this is not a city price.
3 hospitals · 4 doctors
Hyderabad
$18,000–$42,000
India planning band — not a city quote
Typical stay 3–7 nights typical
No verified Hyderabad-only tariff is stored for TAVR or TAVI. Use $18,000–$42,000 as the national planning range until a named hospital issues an itemized estimate; this is not a city price.
4 hospitals · 26 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for TAVR or TAVI
What should international patients budget beyond the cardiac procedure?
A complete TAVR or TAVI budget extends beyond $18,000–$42,000. Include remote review, tests outside the estimate, companion travel, nearby lodging, medicines, rehabilitation, complication contingency and follow-up at home.
Travel follows written clinical acceptance and an itemized estimate. A visa invitation, directory profile or scheduled consultation is not medical clearance.
- Record and imaging review
- The Structural Heart Team specialist reviews diagnosis, source imaging, prior treatment and current stability.
- Multidisciplinary decision
- Confirm indication, alternatives, approach and what could alter or cancel TAVR or TAVI.
- Itemized clinical estimate
- Match professional, facility, implant or graft, ICU, ward, investigation and complication assumptions.
- Arrival and reassessment
- Repeat examination, imaging, laboratory and anaesthetic assessment as clinically indicated before final consent.
- Procedure and critical care
- In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction. Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function.
- Ward recovery and rehabilitation
- After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness.
- Nearby review and handover
- Review wounds, rhythm, medicines and travel fitness, then provide records. Follow-up includes access-site and rhythm review, echo assessment and valve surveillance. Antiplatelet or anticoagulant treatment depends on bleeding risk and other indications; patients should not self-combine therapies.
- Treatment episode$18,000–$42,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay3–7 nights typical typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for TAVR or TAVI in India involve?
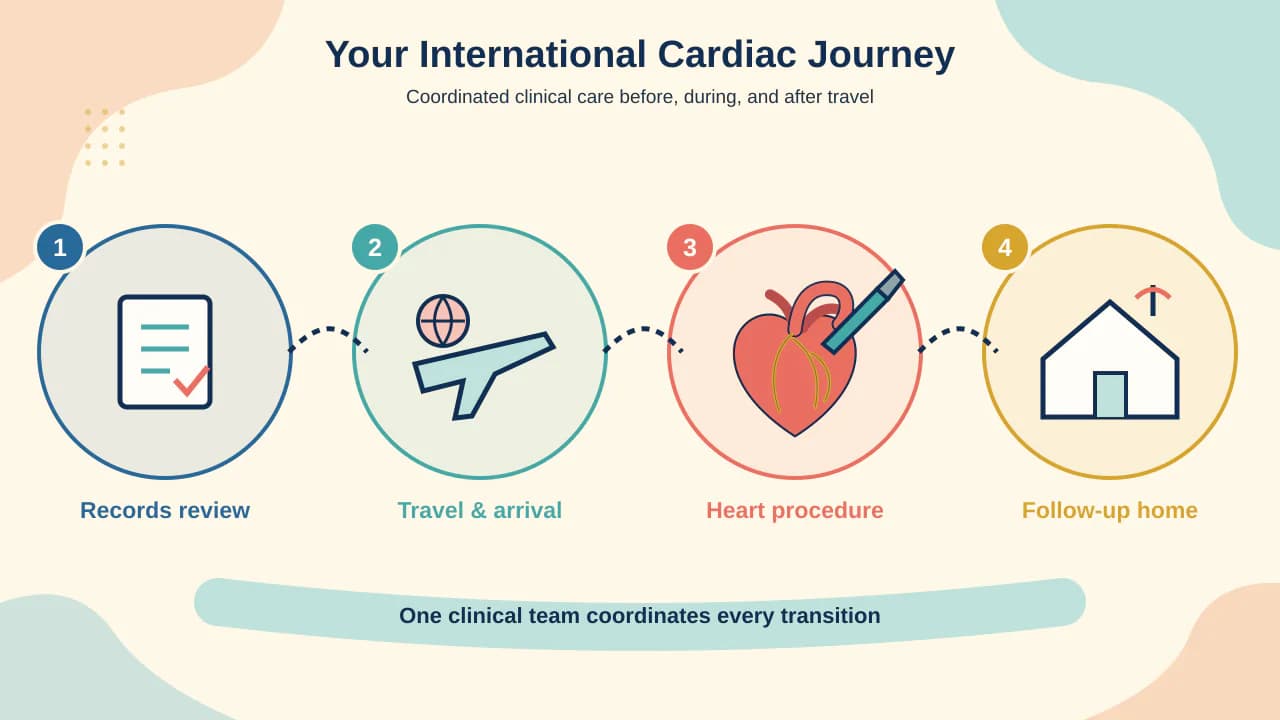
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Send complete records
Complete echocardiogram source images; ECG-gated TAVR CT files and report; Coronary angiography or CT coronary assessment; Peripheral vascular imaging; ECG, rhythm, kidney-function and prior-valve records.
Obtain named-team review
A Structural Heart Team specialist confirms whether the records support further assessment and whether travel appears reasonable.
Discuss indication and alternatives
TAVR is not open surgery and is not suitable for every valve or patient. Active infection, unsuitable annulus or access, need for other cardiac surgery, unfavorable coronary or root anatomy, or durability priorities may favor surgery or another plan. Ask what new finding could change or cancel the plan.
Confirm exact entity mapping
Use only clinicians and hospitals currently mapped to TAVR/TAVI (Transcatheter Aortic Valve Replacement); if none are mapped, leave entity cards empty rather than borrowing generic cardiac listings.
Compare itemized estimates
Use matching clinical assumptions and compare implants, grafts, operating resources, ICU days, exclusions and escalation terms.
Arrange documents and funding
Complete visa, companion, payment and contingency arrangements without treating a visa letter as clinical acceptance.
Book flexible travel and lodging
Use refundable flights and accessible lodging near the exact campus, allowing enough time for preoperative reassessment.
Repeat assessment after arrival
Echo confirms valve severity; ECG-gated TAVR CT sizes the annulus, assesses calcium, coronary heights, root and iliofemoral access. Coronary, renal, rhythm, frailty, dental or infection and surgical assessments complete Heart Team review.
Give informed consent
Review the planned approach, alternatives, uncertainty, procedure-specific risks and the possibility that TAVR or TAVI cannot proceed as expected.
Complete treatment and monitored recovery
In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction. Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function.
Learn discharge care
The patient and caregiver review wounds, medicines, mobility, diet, rehabilitation, warning signs and emergency contacts.
Complete nearby review
Remain nearby until the team reviews early recovery and explicitly discusses fitness to fly.
Carry a complete handover
Take the operative or procedure note, implant and graft details, imaging, discharge summary, medicine list and follow-up plan.
Continue care at home
Follow-up includes access-site and rhythm review, echo assessment and valve surveillance. Antiplatelet or anticoagulant treatment depends on bleeding risk and other indications; patients should not self-combine therapies.
Documents to prepare
- Complete echocardiogram source images
- ECG-gated TAVR CT files and report
- Coronary angiography or CT coronary assessment
- Peripheral vascular imaging
- ECG, rhythm, kidney-function and prior-valve records
- Current medication list, including anticoagulants and antiplatelet medicines
- Allergies, blood group, recent blood tests and infection history
- Passport, visa and companion documents needed for travel
Clinical detail
How the procedure is performed
In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction.
Possible forms include Transfemoral TAVR, Alternative-access TAVR, Surgical AVR instead. They are not interchangeable quote labels.
Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function. The stated procedure time is often about 1–3 hours, with planning and monitored recovery outside procedure time.

Main variations
- Transfemoral TAVR
- Preferred when iliofemoral access is suitable; closure devices and vascular backup are part of planning.
- Alternative-access TAVR
- Used selectively when femoral access is unsuitable; route and invasiveness vary and must be explicit.
- Surgical AVR instead
- May be more appropriate for younger patients, unfavorable anatomy, bicuspid or aortic disease, endocarditis or needed CABG/other surgery.
Preparation
Echo confirms valve severity; ECG-gated TAVR CT sizes the annulus, assesses calcium, coronary heights, root and iliofemoral access. Coronary, renal, rhythm, frailty, dental or infection and surgical assessments complete Heart Team review.
The receiving Structural Heart Team specialist should review complete source imaging, reconcile anticoagulants, antiplatelets and other medicines, assess infection and organ function, and explain alternatives and consent.
Do not stop anticoagulation or antiplatelet treatment without the prescribing and procedural teams. New chest pain, fainting, breathlessness, fever or instability requires prompt local assessment rather than waiting for travel.
Hospital stay and recovery
Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function. After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness.
The catalog stay 3–7 nights typical is an orientation, not a discharge date. Wound condition, rhythm, oxygen need, kidney and neurological function, mobility and reliable medicines affect readiness.
Risks include death, stroke, major vascular injury or bleeding, annular rupture, coronary obstruction, paravalvular leak, valve malposition or embolization, kidney injury, infection and new conduction block requiring a permanent pacemaker.
Follow-up includes access-site and rhythm review, echo assessment and valve surveillance. Antiplatelet or anticoagulant treatment depends on bleeding risk and other indications; patients should not self-combine therapies. Seek urgent clinical help for sudden breathlessness, chest pain, fainting, new weakness or speech change, a painful or enlarging access-site swelling, bleeding, fever, slow or unstable pulse; follow the treating team's own emergency thresholds.
How to compare TAVR/TAVI (Transcatheter Aortic Valve Replacement) quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is TAVR or TAVI being considered now, and what are the alternatives?
- Which imaging, anatomy or physiological finding drives the recommendation?
- Who is the named Structural Heart Team specialist responsible for the plan?
- At which exact campus will the procedure and critical care occur?
- Does the quotation use the exact catalog procedure name?
- What could postpone, change or cancel treatment after arrival?
- Which consultations, imaging and laboratory tests are included?
- Which anaesthesia, perfusion, catheter-lab or hybrid-room resources are included?
- Which grafts, prostheses, devices, patches or conduits are assumed?
- Which blood products and routine inpatient medicines are included?
- How many ventilation, ICU and ward days are allowed?
- How are extra days, major bleeding, infection, organ support and reintervention billed?
- Which surgeon, anaesthetist, perfusion, imaging or other professional fees are separate?
- Which discharge medicines, rehabilitation and first follow-up are included?
- What anticoagulation or antiplatelet plan applies before and after treatment?
- What warning signs require immediate local care or return to the hospital?
- What caregiver skills and accessible accommodation are required?
- When and by whom will fitness to fly be assessed?
- Which records and implant identifiers will be supplied at discharge?
- Who accepts clinical responsibility after the patient returns home?
- Which valve platform and size does CT support?
- Is transfemoral access feasible and what is the backup route?
- What are the coronary-obstruction, vascular and pacemaker plans?
- Why is TAVR preferred over surgical AVR for this patient?
- Does the estimate include planning CT, closure devices and a pacemaker contingency?
Frequently asked questions
How much does TAVR or TAVI cost in Mumbai?
Use $18,000–$42,000 as the stored national planning range. This article has no verified Mumbai-only tariff; an itemized estimate follows clinical record review.
Which Mumbai clinician should review TAVR or TAVI?
A named Structural Heart Team specialist should lead or review the case. Cards appear only for exact live mappings; placement is not a ranking or an experience claim.
Where should the patient stay in Mumbai?
Stay on the same side of the harbour as the confirmed hospital and keep the return booking changeable until the postoperative review. Mumbai and Navi Mumbai are not interchangeable bases. Peak traffic, harbour crossings and monsoon disruption can delay pre-admission testing or an urgent return after discharge.
When can the patient fly home?
There is no universal date. After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness. The treating team must confirm stability and fitness to fly.
What should the written estimate identify?
It should identify TAVR/TAVI (Transcatheter Aortic Valve Replacement), the named team and campus, clinical assumptions, implants or grafts, ICU and ward allowances, exclusions, complication terms and planned follow-up.
How much does TAVR or TAVI cost in India?
TAVR/TAVI (Transcatheter Aortic Valve Replacement) is typically planned at $18,000–$42,000. This national catalog range is not a quotation; anatomy, approach, implants, ICU use and hospital terms determine the final bill.
What is TAVR or TAVI?
TAVR, also called TAVI, treats selected severe aortic stenosis by delivering a collapsible tissue valve through a catheter, most often from the femoral artery, without open-heart valve replacement.
When is TAVR or TAVI considered?
It may be considered for severe symptomatic aortic stenosis and selected other guideline-supported settings after a multidisciplinary Heart Team weighs age, life expectancy, surgical risk, anatomy, durability and patient goals.
Who may need a different plan or delay?
TAVR is not open surgery and is not suitable for every valve or patient. Active infection, unsuitable annulus or access, need for other cardiac surgery, unfavorable coronary or root anatomy, or durability priorities may favor surgery or another plan.
What evaluation is needed before acceptance?
Echo confirms valve severity; ECG-gated TAVR CT sizes the annulus, assesses calcium, coronary heights, root and iliofemoral access. Coronary, renal, rhythm, frailty, dental or infection and surgical assessments complete Heart Team review.
How is the procedure performed?
In a catheter or hybrid laboratory, the team advances a crimped bioprosthetic valve—usually transfemorally—and deploys it within the diseased aortic valve under imaging, with immediate assessment of gradient, leak, coronary flow and conduction.
Which approaches may be discussed?
Transfemoral TAVR, Alternative-access TAVR, Surgical AVR instead. Selection is clinical, not a package upgrade.
How long does the procedure and admission take?
often about 1–3 hours, with planning and monitored recovery outside procedure time. The stored 3–7 nights typical is a broad travel guide, not a promised discharge date.
What are the important risks?
Risks include death, stroke, major vascular injury or bleeding, annular rupture, coronary obstruction, paravalvular leak, valve malposition or embolization, kidney injury, infection and new conduction block requiring a permanent pacemaker.
What can change the estimate?
Important drivers include valve platform and size, transfemoral versus alternative access, coronary and annular anatomy, pacemaker and vascular risk, renal function and contrast planning.
What does early recovery involve?
Monitoring may occur in a cardiac ICU or high-dependency setting and focuses on access bleeding, vascular injury, stroke, rhythm and heart block, valve function, coronary flow and kidney function. After uncomplicated transfemoral treatment, mobilization may begin early, but access healing, rhythm observation and follow-up echo govern discharge; catheter treatment does not guarantee next-day flight fitness.
When can an international patient fly home?
Only after the treating team reviews clinical stability, wounds or access site, rhythm, oxygenation, mobility and the follow-up plan; there is no universal date.
What follow-up is required?
Follow-up includes access-site and rhythm review, echo assessment and valve surveillance. Antiplatelet or anticoagulant treatment depends on bleeding risk and other indications; patients should not self-combine therapies.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Aortic Valve Replacement cost in India
$7,000–$18,500 · stay 8–16 nights
Heart Valve Replacement cost in India
$7,000–$18,000 · stay 8–16 nights
Aortic Root Replacement cost in India
$10,000–$24,000 · stay 10–18 nights
Minimally Invasive Cardiac Surgery cost in India
$8,000–$20,000 · stay 5–12 nights
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 12 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
TAVR/TAVI (Transcatheter Aortic Valve Replacement) cost sheet · All treatment costs in India · Cardiology costs



