
Last updated: 15 September 2026 · Content curated by Dr. Shabnam Choudhary · Medically reviewed by Dr. Saffiyyah Chaudhary
Quick Answer
Thyroidectomy for Thyroid Cancer in Bengaluru is planned against $4,000–$10,000, with 2–4 nights stored only for broad trip planning. Neither figure is a city tariff, an acceptance promise or a recommendation.
Through a low collar incision under general anaesthesia the surgeon identifies and protects the recurrent laryngeal nerves and parathyroid glands, divides the thyroid blood supply and removes the planned lobe or whole gland, dissecting node levels only where staging indicates. Admission is frequently two to four nights, watching airway safety, drain output, voice and calcium.
- India cost range
- $4,000–$10,000
- Typical starting point
- $4,000
- Typical hospital stay
- 2–4 nights
- Procedure time
- commonly 2–4 hours, longer when neck node levels are dissected
- Recovery
- Two to four nights typical
Major cost factors: extent of thyroid resection, neck node dissection, nerve monitoring and devices, calcium and hormone management. International patients should also budget for accommodation, airport transfers, a medical visa, medicines and follow-up.
Often quoted separately: changed resection scope; complications and escalation; extended pathology; adjuvant treatment; rehabilitation and devices.
Why request a cost through GAF rather than a hospital?
Writing to one campus gets you that campus’s package. A GAF request is reviewed against your records and returned as suitable doctor and hospital options with an indicative, itemised estimate. There is no obligation to book.
- Doctor review first. The number follows a reading of your imaging, test results and clinical records, not a brochure range.
- Hospital options. You can compare listed campuses before you travel, instead of starting over with each international desk.
- International-patient coordination. Visa letters, records routing and companion logistics sit with the same request.
Thyroidectomy for Thyroid Cancer in Bengaluru
It is generally discussed when cytology indicates thyroid cancer, or when a known cancer is growing, pressing on the airway or has spread to neck nodes. Some very low-risk papillary cancers are instead monitored under specialist protocols. Planning rests on neck ultrasound mapping the nodule and node levels, a fine-needle aspiration cytology category, and vocal cord assessment where voice change or extensive disease is suspected. Cross-sectional imaging is added for bulky disease and calcitonin testing where medullary cancer is suspected.
Several listed campuses keep cancer surgery, radiation and medical oncology in one building, which suits patients completing a whole sequence in a single visit. Confirm the named surgical oncologist or head and neck surgeon who operates on the thyroid, the exact operating campus, where histopathology is reported and which team reviews the result with you.
The airport sits well north of most hospital districts, so the first transfer is the longest of the five cities and cross-city traffic can turn a routine review into a long seated journey after surgery. A lift-accessible stay near the operating campus is more useful than an airport hotel. Plan simple meals, a companion and level walking space for early mobilisation.
Doctor and hospital cards for Bengaluru resolve only from exact live CMS relationships for Thyroidectomy for Thyroid Cancer. If that exact relationship is absent, cards must remain empty; a general Surgical Oncology or cancer-centre label cannot verify current case acceptance for this operation. That is a catalog gap, not a ranking or availability claim.
Send complete oncology records before booking non-refundable travel to Bengaluru. A remote opinion can change after examination, repeat imaging, anaesthetic assessment or pathology review.
What thyroidectomy for thyroid cancer typically costs in Bengaluru
The estimate can change with extent of thyroid resection, neck node dissection, nerve monitoring and devices, calcium and hormone management. These are clinical and resource differences rather than premium upgrades.
Ask for the resection and nodal scope, the named surgeon, anaesthesia, pathology plan, ward nights, intensive-care assumption, complication terms, exclusions and follow-up in writing.
Budget separately for travel through Kempegowda International Airport, lodging near the campus, a companion, meals, take-home medicines and extra nights if pathology or recovery delays departure.
What moves the quote in Bengaluru
- Extent of thyroid resection
- Lobectomy, total thyroidectomy and completion surgery are different operations.
- Neck node dissection
- Central or lateral dissection lengthens surgery, adds a drain and changes monitoring.
- Nerve monitoring and devices
- Nerve monitoring and energy devices are equipment charges that vary by campus.
- Calcium and hormone management
- Serial calcium testing, supplementation and hormone titration are often omitted from estimates.
Medical travel through Bengaluru
Send the biopsy report, slides or blocks where your laboratory releases them, imaging files, prior treatment summaries and current laboratory results before travelling to Bengaluru.
Obtain written acceptance from a named surgeon, and confirm anaesthesia cover, blood bank access, intensive-care support and any reconstructive or rehabilitation service the plan needs.
Recovery is judged on calcium levels, voice, swallowing and wound healing rather than a fixed calendar, with hormone dosing reviewed once the gland is removed. A mild climate makes short outdoor walks more comfortable during a multi-week stay, but it does not reduce the risk of bleeding, infection, chest complications or venous thromboembolism. Travel home only after the team documents clinical stability and a written follow-up plan.
Hospitals and units listed in Bengaluru
Doctor and hospital cards for Bengaluru resolve only from exact live CMS relationships for Thyroidectomy for Thyroid Cancer. If that exact relationship is absent, cards must remain empty; a general Surgical Oncology or cancer-centre label cannot verify current case acceptance for this operation. That is a catalog gap, not a ranking or availability claim.
Confirm the exact campus, operating surgeon, resection and nodal scope, frozen-section policy, pathology handover and an emergency contact in writing. General accreditation does not establish current capability for a specific cancer operation.
Thyroidectomy for Thyroid Cancer doctors in Bengaluru · Thyroidectomy for Thyroid Cancer hospitals in Bengaluru · Thyroidectomy for Thyroid Cancer cost in India
What Is Thyroidectomy for Thyroid Cancer?
The thyroid sits in two lobes in front of the windpipe. The recurrent laryngeal nerves that move the vocal cords run close behind it and the four parathyroid glands controlling calcium sit on or beside it, so preserving those structures is part of the operation.
Lobectomy may suffice for a small, low-risk cancer in one lobe, while total thyroidectomy is usual for larger, multifocal or higher-risk disease and is what makes radioiodine treatment possible. Node levels are added only where staging shows involvement or material risk.
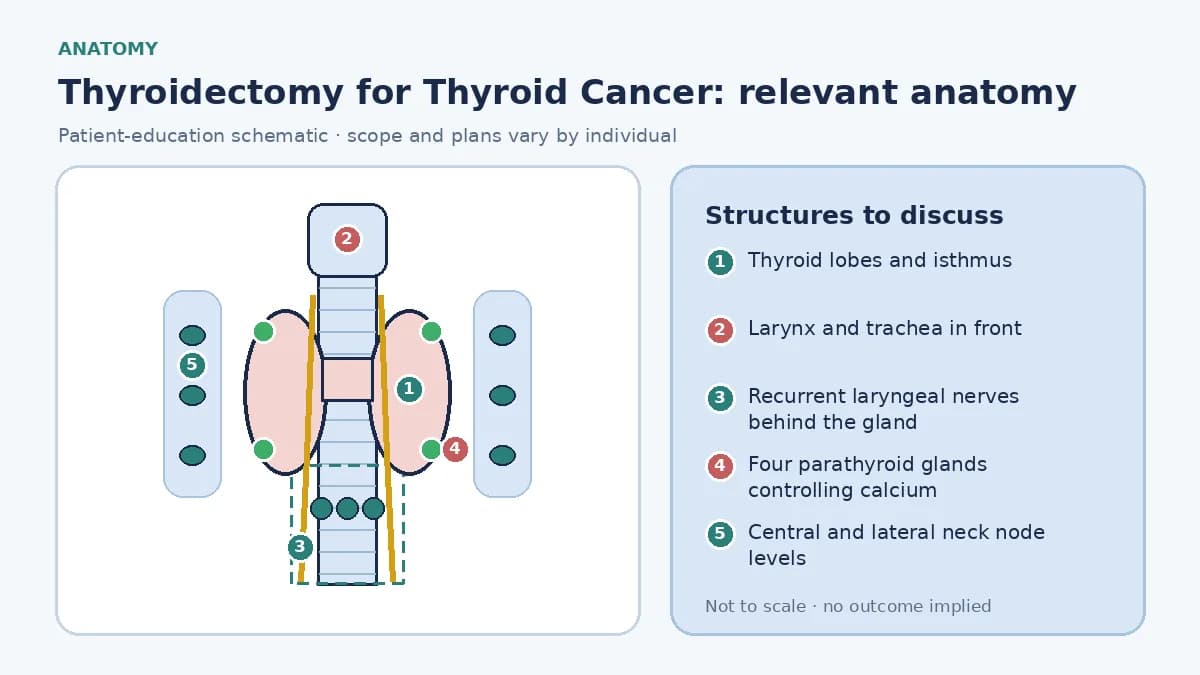
When Might Thyroidectomy for Thyroid Cancer Be Considered?
A qualified surgical oncologist or head and neck surgeon who operates on the thyroid must assess suitability, normally with multidisciplinary review. Decisions usually involve the surgeon, a pathologist, a radiologist reading the ultrasound, an endocrinologist for hormone and calcium management, and a nuclear medicine physician where radioiodine is considered.
A remote opinion can change after examination and repeat imaging.
How the operation is performed, recovery and variations →
Thyroidectomy for Thyroid Cancer cost in India
The $4,000–$10,000 value is GAF's stored national planning range for thyroidectomy for thyroid cancer, not a fixed package. Replace it with an itemized quotation naming the surgical oncologist or head and neck surgeon who operates on the thyroid, the campus, the planned resection and nodal scope, the expected nights and the pathology plan.
Cost moves with extent of thyroid resection, neck node dissection, nerve monitoring and devices, calcium and hormone management, stage and local extent, previous cancer treatment, pathology depth, anaesthesia and medical risk, facility and admission scope, unplanned escalation. A limited resection is not comparable with radical surgery or with difficult anatomy after previous treatment.
Do not derive city tariffs from the national band. Keep $18,000–$40,000, flights, visas, transport, lodging, medicines, extra nights and a complication contingency in the same budget.
Costing the operation alone is the commonest budgeting error, because pathology, adjuvant treatment and rehabilitation are separate pathways with separate estimates.
Planning Range ≠ Final Hospital Quotation. Records review and qualified surgical, oncology and anaesthetic assessment come before any itemized offer.
Thyroidectomy for Thyroid Cancer cost breakdown in India
Component prices are rarely published as a public tariff. The lines below describe what typically sits inside a surgical estimate, not a dollar amount for each row.
- Surgeon and assistant fees
- The named operating team.
- Theatre and anaesthesia
- Operating room time and anaesthesia.
- Consumables and devices
- Staplers, energy devices, drains, implants.
- Ward and critical care
- Room category and high-dependency nights.
- Histopathology
- Margin and nodal reporting.
- Imaging and laboratory
- Inpatient scans, tests, blood products.
- Medicines during admission
- Analgesia, antibiotics, thromboprophylaxis.
Planning range or quotation?
The $4,000–$10,000 figure is an indicative planning range. A final hospital quotation is itemised, issued after a consultant reviews your records, and still subject to what is found clinically.
Get a Personalized Cost Estimate
What is usually included in a Thyroidectomy for Thyroid Cancer package?
No two hospitals draw the line in the same place, so read an estimate for what it excludes as carefully as for what it covers. The pattern below is what listed campuses typically bundle into a surgical estimate for this procedure. Anything not written into your estimate should be assumed to be extra until the hospital confirms otherwise.
Usually included
Usually included
Preoperative assessment
Surgeon and anaesthesia review where itemized.
Usually included
The consented operation
Surgeon, theatre, consented scope.
Usually included
Anaesthesia and routine medicines
Anaesthesia and stated monitoring.
Usually included
Hospital recovery as quoted
Stated ward nights and room category.
Usually included
Routine histopathology
Standard specimen and nodal reporting.
Usually included
Discharge documents
Operation note, summary, early review.
Usually included
Named operative plan
Only the stated thyroidectomy for thyroid cancer scope and approach are included.
May be charged separately
May be separate
Changed resection scope
Wider excision, extra nodal levels, unlisted reconstruction.
May be separate
Complications and escalation
Transfusion, intensive care, re-operation, longer stay.
May be separate
Extended pathology
Frozen section, immunohistochemistry, molecular panels.
May be separate
Adjuvant treatment
Chemotherapy, targeted therapy, radiotherapy, radioiodine.
May be separate
Rehabilitation and devices
Therapy, prostheses, dental work, medicines.
May be separate
Travel and living
Flights, visas, transport, lodging, companion.
Catalog inclusions listed for this pathway: surgical oncology consultation and records review; named surgeon on camera before travel; theatre, anaesthesia and inpatient stay as quoted; histopathology of the specimen; discharge summary to your home oncologist.
What can increase the cost?
These are the drivers that actually move a bill for this operation, in rough order of how often they do it. Most of them are clinical decisions rather than commercial ones, which is why an honest estimate is written after a records review rather than before it.
- Extent of thyroid resection
- Lobectomy, total thyroidectomy and completion surgery are different operations.
- Neck node dissection
- Central or lateral dissection lengthens surgery, adds a drain and changes monitoring.
- Nerve monitoring and devices
- Nerve monitoring and energy devices are equipment charges that vary by campus.
- Calcium and hormone management
- Serial calcium testing, supplementation and hormone titration are often omitted from estimates.
- Stage and local extent
- Invasive disease lengthens surgery and widens the resection.
- Previous cancer treatment
- Earlier chemotherapy or radiation alters tissue planes and risk.
- Pathology depth
- Frozen section and molecular testing are separate charges.
- Anaesthesia and medical risk
- Comorbidity changes monitoring and length of stay.
- Facility and admission scope
- Ward and intensive-care nights are different scopes.
- Unplanned escalation
- A complication or return to theatre changes the episode.
Cancer-specific surgical planning for Thyroidectomy for Thyroid Cancer
Planning rests on neck ultrasound mapping the nodule and node levels, a fine-needle aspiration cytology category, and vocal cord assessment where voice change or extensive disease is suspected. Cross-sectional imaging is added for bulky disease and calcitonin testing where medullary cancer is suspected.
Earlier chemotherapy, radiation or surgery alter tissue planes and operative risk, so those records matter as much as the current scan.
Margins, lymph nodes and what pathology decides
The specimen is examined for tumour type, size, multifocality, extension beyond the capsule, vascular invasion and the number of involved nodes. That report, not the operation, decides whether radioiodine, hormone suppression targets or further surgery are advised.
A cancer operation is judged on margin clearance and assessment of the nodes at risk, not on the size of the incision.
When the planned operation changes during surgery
A lobectomy can become a total thyroidectomy if findings or frozen section show more extensive disease, and unexpected nodal involvement can extend the operation into a formal neck dissection. Consent and the quotation should both allow for that.
Multidisciplinary care and treatment sequencing
Surgery is usually the first treatment, with radioiodine, thyroid hormone suppression and occasionally external radiation or systemic therapy considered afterwards on the basis of final histopathology and risk category.
Ask who owns each step and who decides the next one: treatment before surgery can change what operation is possible.
Function, rehabilitation and what may change permanently
Total thyroidectomy commits a patient to lifelong thyroid hormone replacement with regular blood monitoring. Voice change is usually temporary but can persist, and calcium supplementation is occasionally needed long term when parathyroid glands are damaged.
Rehabilitation is part of the treatment, yet it is frequently excluded from surgical estimates. Confirm what is included and what continues at home.
Follow-up, surveillance and international travel
A local endocrinologist or oncologist should receive the operation note, discharge summary and histopathology, then manage hormone dosing, calcium, thyroglobulin monitoring, neck ultrasound surveillance and any radioiodine decision. Discharge from the ward is not the same as clearance to fly.
Thyroidectomy for Thyroid Cancer cost: India vs other medical tourism destinations
India and United States values are stored GAF catalog ranges. Other countries need direct quotations, because comparable cancer-surgery packages are not held in the catalog.
A meaningful comparison holds diagnosis, resection and nodal scope, surgeon, facility, pathology depth and ward nights constant.
Swipe to compare destinations →
| Country | Approximate cost | Relative cost position | Important cost considerations |
|---|---|---|---|
| India | $4,000–$10,000 | Baseline | GAF catalog planning range. The stored India figure is a national planning range for the operation and its stated admission. It does not establish resectability, surgical scope, nodal plan, reconstruction, pathology depth or a final quotation. |
| Turkey | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Compare the exact resection, nodal dissection, reconstruction, frozen-section policy, intensive-care assumption, ward nights and complication terms rather than a headline cancer-surgery package. |
| Thailand | Confirmation requiredIndicative planning estimate* | Higher than India | Depends on procedure and hospital. International coordination does not by itself establish case acceptance, multidisciplinary review, reconstructive cover or continuity of adjuvant treatment after the patient returns home. |
| United Arab Emirates | Confirmation requiredIndicative planning estimate* | Higher than India | Quotation required. Surgeon, facility, anaesthesia, consumable, histopathology and follow-up charges are frequently billed separately, so a single quoted figure may not be the comparable one. |
| Singapore | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Request a self-pay estimate tied to the specific cancer, the planned resection and nodal scope and the expected admission. Subsidised local billing and private international billing differ. |
| Germany | Confirmation requiredIndicative planning estimate* | Higher than India | Varies significantly. Eligibility, professional billing, pathology scope and post-travel oncology follow-up need direct confirmation. Inpatient norms after major cancer surgery are often longer than in self-pay markets. |
| United Kingdom | Confirmation requiredIndicative planning estimate* | Higher than India | Private self-pay varies. Overseas patients should verify acceptance, quotation boundaries, emergency access and who reviews final histology and decides adjuvant treatment once they have travelled home. |
| United States | $18,000–$40,000 | ≈4.1× India | Stored self-pay reference. Facility, surgeon, anaesthesia, pathology and follow-up charges are usually separate, and $18,000–$40,000 is a comparison range for the operation rather than a bundled cancer-treatment quotation. |
Comparisons are indicative and may not represent identical operations. Tumour extent, added resection, complications, currency and length of stay change the final amount.
The point of this table is not that one country is better. Cost level and treatment-market structure are different things. Compare the named hospital, multidisciplinary support, included care and follow-up pathway as carefully as the headline figure.
Which destination is right for you?
Use this only as a reading guide for the table above. It is not a medical recommendation, and it does not rank countries.
Looking for the lowest overall treatment cost?
IndiaLooking for premium private hospital infrastructure?
Singapore / UAELooking for proximity from the Middle East?
UAE / India / TurkeyLooking for established European oncology systems?
Germany / UK
Why do international patients consider India for thyroidectomy for thyroid cancer?
Patients evaluate India for access to a named surgical oncologist or head and neck surgeon who operates on the thyroid, multidisciplinary cancer services in one city, and a self-pay planning range below the stored United States reference. Cost alone is not a clinical reason to travel.
What matters is individual acceptance, procedure-specific experience, intensive-care support, histopathology quality, reconstructive cover where relevant, and who continues adjuvant treatment.
No provider is ranked here and no outcome is promised. Unstable illness, or treatment already under way locally, can make an elective trip inappropriate.
Thyroidectomy for Thyroid Cancer hospitals in Bengaluru
Cards follow exact CMS relationships for Thyroidectomy for Thyroid Cancer. Accreditation alone does not establish current case acceptance.
Apollo Hospitals, Bannerghatta Road
 JCI Accredited
 NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
1 listed doctor for this pathway
Languages listed: English, Kannada, Hindi
Gleneagles Hospitals, Bengaluru
- JCI Accredited
- NABH Accredited
 NABL Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
Consultant match on request
Languages listed: English, Kannada, Hindi
Medicover Hospital, Bengaluru
- JCI Accredited
- NABH Accredited
- Radiation Oncology
- Surgical Oncology
- Medical Oncology
- Hematology
Consultant match on request
Languages listed: English, Kannada, Hindi
Thyroidectomy for Thyroid Cancer hospitals in Bengaluru · Talk to a treatment coordinator
Surgical oncologists for Thyroidectomy for Thyroid Cancer in Bengaluru
Profiles appear only where Thyroidectomy for Thyroid Cancer is an exact current CMS relationship. Placement is not a ranking or an outcome claim.

Dr. Monisha P
Surgical Oncology
9+ Years Experience
Oral Cancer Surgery · Laryngeal Cancer Surgery · Hypopharyngeal Cancer Surgery
English, Kannada, Hindi
Thyroidectomy for Thyroid Cancer doctors in Bengaluru (1 listed) · Get a personalized cost estimate
Thyroidectomy for Thyroid Cancer cost by city in India
The five listed cities retain $4,000–$10,000 because no verified city tariffs are stored. Their overlays add airport geography, climate, lodging and recovery logistics rather than local prices.
Cards resolve only from CMS entities carrying the exact Thyroidectomy for Thyroid Cancer relationship, so missing mappings leave cards empty.
Swipe to compare Indian cities →
Delhi NCR
$4,000–$10,000
India planning band — not a city quote
Typical stay 2–4 nights
No verified Delhi NCR-only tariff is stored for thyroidectomy for thyroid cancer. Use $4,000–$10,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
15 hospitals · 8 doctors
Mumbai
$4,000–$10,000
India planning band — not a city quote
Typical stay 2–4 nights
No verified Mumbai-only tariff is stored for thyroidectomy for thyroid cancer. Use $4,000–$10,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
5 hospitals · 2 doctors
Bengaluru
$4,000–$10,000
India planning band — not a city quote
Typical stay 2–4 nights
No verified Bengaluru-only tariff is stored for thyroidectomy for thyroid cancer. Use $4,000–$10,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
3 hospitals · 1 doctor
Chennai
$4,000–$10,000
India planning band — not a city quote
Typical stay 2–4 nights
No verified Chennai-only tariff is stored for thyroidectomy for thyroid cancer. Use $4,000–$10,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
5 hospitals · 3 doctors
Hyderabad
$4,000–$10,000
India planning band — not a city quote
Typical stay 2–4 nights
No verified Hyderabad-only tariff is stored for thyroidectomy for thyroid cancer. Use $4,000–$10,000 as the national planning range until a named provider issues an itemized estimate; it is not a city price.
6 hospitals · 7 doctors
Costs vary considerably by hospital, specialist, clinical complexity, insurance, room or day-care category, and what is included in the package.
Choosing a city for thyroidectomy for thyroid cancer
Patients usually pick the treating team first and the city second. The city still affects daily travel, accommodation, companion arrangements and access to follow-up. Here is what genuinely differs between the five cities we list.
What should international patients budget beyond the surgery?
The surgical estimate is only one line in a medical-travel budget. The rows below separate hospital charges from living and travel costs so you can plan without treating a brochure package as a trip total.
- Treatment episode$4,000–$10,000
- Pre-operative testsOften inside the estimate — confirm
- Hospital stay2–4 nights typically bundled
- Additional procedures or extended careQuoted separately if advised
- Accommodation for companionVaries by city and length of stay
- Local transportationAirport and daily hospital transfers
- FlightsDepends on origin
- Medical visaFee set by the issuing consulate
Planning estimate — not a hospital quotation.
Get a Personalized Treatment Estimate
What does medical travel for thyroidectomy for thyroid cancer in India involve?
The sequence below is how a records-first pathway normally runs. The order matters: everything before arrival exists so that you are not making decisions in an unfamiliar hospital corridor with a suitcase beside you.
Submit records
Biopsy, imaging files, treatment summaries, laboratory results.
Specialist review
A named surgical oncologist or head and neck surgeon who operates on the thyroid reads imaging and pathology.
Pathology verification
Local slide review can change diagnosis or grade.
Staging assessment
Remaining imaging or nodal sampling.
Multidisciplinary opinion
Surgery, oncology and pathology together.
Written treatment plan
Intent, resection scope, nodal plan, admission.
Itemized cost estimate
Surgery and stay quoted apart from adjuvant therapy.
Medical visa and travel
An invitation letter supports the visa.
Arrival and reassessment
Examination, repeat tests, anaesthetic clearance, consent.
Surgery
The consented thyroidectomy for thyroid cancer and planned monitoring.
Monitored recovery
Ward care, mobilisation, wound and drain review.
Pathology review
Margins, nodes and further testing discussed.
Return home and handover
Documents, medicines, a named clinician for follow-up.

Documents to prepare
- Neck ultrasound report and images mapping the nodule and node levels
- Fine-needle aspiration cytology report with its reporting category
- Thyroid function, calcium and vitamin D results
- Imaging files on a disc or drive rather than screen photographs
- Paraffin blocks or slides where the home laboratory releases them
- Summaries of previous chemotherapy, immunotherapy, targeted therapy or radiation
- Operative notes from earlier cancer or regional surgery
- Current medicines, allergies and previous anaesthetic problems
- Recent blood count, kidney and liver results
- Passport, visa and companion details
Clinical detail
How the operation is performed
Through a low collar incision under general anaesthesia the surgeon identifies and protects the recurrent laryngeal nerves and parathyroid glands, divides the thyroid blood supply and removes the planned lobe or whole gland, dissecting node levels only where staging indicates.
The specimen goes to histopathology. Theatre time is commonly 2–4 hours, longer when neck node levels are dissected.
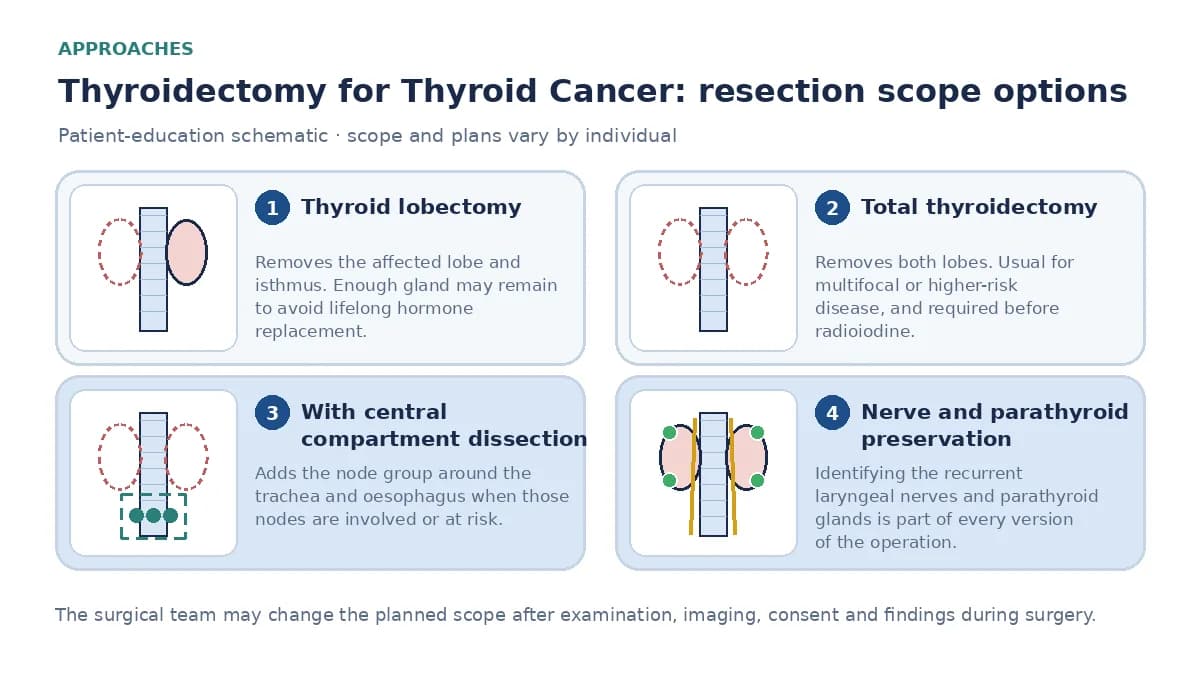
Main variations
- Thyroid lobectomy
- Removes the affected lobe and isthmus, sometimes preserving enough gland to avoid lifelong hormone replacement.
- Total thyroidectomy
- Removes the whole gland; normally required before radioiodine and usual for multifocal or higher-risk disease.
- With central compartment dissection
- Adds the node group around the trachea and oesophagus when those nodes are involved or at risk.
- With lateral neck dissection
- Adds lateral node levels when imaging or biopsy confirms disease there, lengthening surgery.
- Nerve-monitored open surgery
- Intraoperative nerve monitoring used alongside direct identification of the recurrent laryngeal nerve.
Preparation
Assessment commonly includes thyroid function, calcium and vitamin D testing, the ultrasound map and cytology report, vocal cord assessment where indicated, and routine anaesthetic checks. Not every patient needs every test.
Reconcile blood thinners, diabetes medicines, inhalers and allergies before travel. Consent should name the resection scope, the nodal plan and what findings could change either.
Hospital stay and recovery
Admission is frequently two to four nights, watching airway safety, drain output, voice and calcium. Recovery is judged on calcium levels, voice, swallowing and wound healing rather than a fixed calendar, with hormone dosing reviewed once the gland is removed.
Recognised risks include neck haematoma that can threaten the airway, temporary or permanent hoarseness from recurrent laryngeal nerve injury, temporary or permanent low calcium from parathyroid injury, wound infection, and after lateral dissection, shoulder discomfort or a chyle leak.
Seek urgent help for rapid neck swelling, difficulty breathing, worsening voice change, tingling around the mouth or fingers, muscle cramps, fever or wound discharge.
How to compare Thyroidectomy for Thyroid Cancer quotes from Indian hospitals
Print these and work through them on the video call. A house that answers without hedging is telling you something useful about how it will behave when something goes wrong.
- Why is thyroidectomy for thyroid cancer recommended, and what alternatives remain?
- Is the intent curative or symptom control?
- Who is the named surgical oncologist or head and neck surgeon who operates on the thyroid, and at which campus?
- What will be removed, and what will be preserved?
- What function may change permanently?
- What findings could change the consented scope?
- Was this case discussed at a tumour board?
- Is any treatment recommended before surgery?
- Which existing tests are accepted rather than repeated?
- Which surgeon, anaesthesia and facility fees are included?
- Which implants or consumables are assumed?
- Will frozen section be used, and is it included?
- Which histopathology and molecular tests are included?
- Is reconstruction inside this estimate?
- How are transfusion, intensive care and extra nights billed?
- How many nights and which room category are assumed?
- Which rehabilitation follows discharge?
- What warning signs need urgent review before I fly?
- When is histopathology ready, and who explains it?
- Who delivers adjuvant treatment if advised?
- Is the plan a lobectomy or a total thyroidectomy, and what would change it during surgery?
- Are central or lateral neck nodes included in this estimate?
- Is radioiodine treatment quoted separately, and who arranges it?
Why your final Thyroidectomy for Thyroid Cancer cost may be different
This page carries a planning range. A hospital letter is an estimate written against a named operation, surgeon, room category and stated nights, so the two are not expected to match.
If two hospitals quote differently, read the line items before assuming one is overcharging: one may include frozen section and immunohistochemistry while the other bills them later.
A total medical trip costs more than the operation. Flights, visas, transport, lodging, an attendant, medicines, pathology and extra nights sit outside the surgical estimate.
Frequently asked questions
How much does thyroidectomy for thyroid cancer cost in Bengaluru?
Use $4,000–$10,000 as the stored national planning range. No verified Bengaluru-only tariff is stored, so an itemized provider estimate is required before you budget.
Which Bengaluru clinician should assess thyroidectomy for thyroid cancer?
A named surgical oncologist or head and neck surgeon who operates on the thyroid should assess it, usually with multidisciplinary input. Cards appear only for exact live CMS relationships and are not rankings.
Where should an international patient recover in Bengaluru?
A lift-accessible stay near the operating campus is more useful than an airport hotel. Plan simple meals, a companion and level walking space for early mobilisation. The airport sits well north of most hospital districts, so the first transfer is the longest of the five cities and cross-city traffic can turn a routine review into a long seated journey after surgery.
When can an international patient fly home?
There is no universal date. Recovery is judged on calcium levels, voice, swallowing and wound healing rather than a fixed calendar, with hormone dosing reviewed once the gland is removed. The treating team must document fitness to fly.
What should the written estimate identify?
It should name Thyroidectomy for Thyroid Cancer, the planned resection and nodal scope, reconstruction where relevant, pathology, ward nights, intensive-care assumption and complication terms.
How much does thyroidectomy for thyroid cancer cost in India?
$4,000–$10,000 is a national planning range rather than a quotation. Resection scope, nodal dissection, reconstruction, pathology depth and length of stay determine the final bill.
What is thyroidectomy for thyroid cancer?
Thyroidectomy for thyroid cancer removes part or all of the thyroid gland to treat a proven or strongly suspected thyroid malignancy, sometimes with the lymph nodes of the central or lateral neck.
What decides how extensive the operation is?
Lobectomy may suffice for a small, low-risk cancer in one lobe, while total thyroidectomy is usual for larger, multifocal or higher-risk disease and is what makes radioiodine treatment possible.
Which staging is needed before surgery?
Planning rests on neck ultrasound mapping the nodule and node levels, a fine-needle aspiration cytology category, and vocal cord assessment where voice change or extensive disease is suspected.
Who may be considered for this operation?
It is generally discussed when cytology indicates thyroid cancer, or when a known cancer is growing, pressing on the airway or has spread to neck nodes.
How long does thyroidectomy for thyroid cancer take?
Theatre time is commonly 2–4 hours, longer when neck node levels are dissected. Findings and any reconstruction can change it.
How long is the hospital stay?
Admission is frequently two to four nights, watching airway safety, drain output, voice and calcium. Clinical criteria, not a schedule, determine discharge.
What are the important risks?
Recognised risks include neck haematoma that can threaten the airway, temporary or permanent hoarseness from recurrent laryngeal nerve injury, temporary or permanent low calcium from parathyroid injury, wound infection, and after lateral dissection, shoulder discomfort or a chyle leak.
What may change permanently after this surgery?
Total thyroidectomy commits a patient to lifelong thyroid hormone replacement with regular blood monitoring.
Will treatment be needed after the operation?
Surgery is usually the first treatment, with radioiodine, thyroid hormone suppression and occasionally external radiation or systemic therapy considered afterwards on the basis of final histopathology and risk category. Final histopathology usually decides this.
What follow-up is needed after returning home?
A local endocrinologist or oncologist should receive the operation note, discharge summary and histopathology, then manage hormone dosing, calcium, thyroglobulin monitoring, neck ultrasound surveillance and any radioiodine decision.
Dr. Shabnam Choudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She contributes to the curation and development of medically informative healthcare content, helping ensure that information is structured clearly and presented in a patient-friendly manner.
Content Curator
Dr. Shabnam Choudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Dr. Saffiyyah Chaudhary, BDS, is a dental professional who graduated from Al-Ameen Medical College, Bijapur, Karnataka. She provides medical review of healthcare content to help ensure that clinical information is accurate, understandable, and appropriately presented for patients and their families.
Medically Reviewed By
Dr. Saffiyyah Chaudhary
BDS
Al-Ameen Medical College, Bijapur, Karnataka
Rajiv Gandhi University of Health Sciences (RGUHS), Bengaluru

Related treatment costs
Neck Dissection cost in India
$4,500–$12,000 · stay 3–6 nights
Sentinel Lymph Node Biopsy cost in India
$2,000–$5,500 · stay 1–2 nights
External Beam Radiotherapy (EBRT) cost in India
$1,000–$6,000+ · stay 15–35 sessions typical · 4–7 weeks
Targeted Therapy cost in India
$8,000–$30,000 · stay Oral or infusion · months of therapy
Cost note
Cost ranges on this page are for preliminary planning and comparison only. The final treatment cost depends on the patient's diagnosis, treatment plan, hospital, doctor, procedure complexity and other clinical factors. A personalized quotation should be obtained before making treatment or travel decisions.
This page is general information about treatment costs and pathways. It is not a diagnosis, a treatment recommendation or a substitute for an individualised medical opinion. Decisions about whether this procedure is appropriate for you belong to a qualified doctor who has reviewed your records.
Last updated 15 September 2026. Cost data is maintained separately from this article and refreshed as listed campuses revise their planning ranges.
Thyroidectomy for Thyroid Cancer cost sheet · All treatment costs in India · Surgical Oncology costs



